💥Mains Ready By December. Smash Mains & Smash PYQ Admissions Open

GS Paper: GS2-13.Issues relating to development and management of Social Sector/Services relating to Health, Education, Human Resources.

  • [25 March 2024] The Hindu Op-ed: TB Control in India Calls for person-centered Solutions

    PYQ Relevance:Mains: 
    Q) “Besides being a moral imperative of a Welfare State, primary health structure is a necessary precondition for sustainable development.” Analyse. ( UPSC IAS/2021) 

    Q) Appropriate local community-level healthcare intervention is a prerequisite to achieving ‘Health for All’ in India. Explain. (UPSC IAS/2018) 

    Prelims:
    In India, the term “Public Key Infrastructure” is used in the context of  (UPSC IAS/2020) 
    a) Digital security infrastructure
    b) Food security infrastructure
    c) Health care and education infrastructure
    d) Telecommunication and transportation infrastructure

    Note4Students: 

    Prelims: Governance; Health Care; TB Elimination Program 2025;

    Mains: Governance; Health Care Syatem in India; Issues  related to TB and measures;

    Mentor comments:  Globally, and in India, tuberculosis (TB) continues to loom large as a public health challenge impacting millions. About 85% of people who develop TB can be successfully treated with drug regimens of 6 months. Universal health coverage (UHC) is necessary to ensure that all those with the disease can access these treatments. Today although India aims for 2025, the recent TB elimination policy in India necessitates person-centered solutions to address the challenges of tuberculosis effectively. 

    Let’s learn. 

    Why in the News?

    On account of World TB Day (March 24), we must recognize the needs and interests of TB patients, and the communities must form the basis of disease elimination.

    Context:

    • The theme for World TB Day 2024: ‘Yes! We can end TB!‘.
    • The MoHFW along with various development partners of the Health Ministry launched the Tuberculosis (TB) Mukt Bharat Abhiyaan in 2021 under the NSP India 2020–25 for TB Elimination in a major mission activity for ending the epidemic of TB by 2025.
    • Despite ambitious goals set by India’s health authorities to eliminate TB, the challenge is huge and progress is not fast enough. 
    Present Scenario:

    National Strategic Plan for Eliminating TB (2020-25): NSP India 2020–2025 intends to accelerate the national response to TB.
    The actions included:

    Provide top-priority reinforcements to the existing workforce;
    Scale up private provider engagement;
    Changes in approach from passive community to active community participation and ownership;
    Investment in TB surveillance staff and systems for accurate, complete and timely information;
    Deployment of new precision diagnostic tools;
    Support patients comprehensively throughout treatment;
    Redesign and pursue targeted active case finding;

    Deploy and evaluate ambitious plans to implement TB preventive treatment in households and other close contacts, children, People living with HIV (PLHIV), and other locally defined “high-risk” groups, using new and short regimens.

    Why there is a need for a person-centered approach to TB care and management?

    1) Need to Understand through shift paradigm:

    • TB as a human crisis: Tuberculosis is one of the ten major causes of mortality worldwide. The trend of increasing TB cases and drug resistance in India is very disturbing.
    • TB as a gendered crisis: Women and other gender minorities living in violently patriarchal societies face unique challenges in accessing timely diagnosis and treatment for TB. It is particularly difficult for gender minorities to seek care due to structural and social barriers, stigma in the health system, and widespread poverty.
    • TB as an economic challenge: The largest indirect cost of TB for a patient is income lost by being too sick to work. Studies suggest that on average three to four months of work time are lost, resulting in average lost potential earnings of 20% to 30% of annual household income.
    • TB as a Social and Environmental Challenge: For centuries, TB has been linked anecdotally with environmental risk factors that go hand-in-hand with poverty: indoor air pollution, tobacco smoke, malnutrition, overcrowded living conditions, and excessive alcohol use.

    2) Care needs to be more Humane 

    • Need for Strengthening Community-Based Care: Efforts are needed to strengthen community-based TB care models, empowering frontline healthcare workers to deliver comprehensive care that is closer to where patients live.
    • Need for Mental Support: This is important as survivor narratives tell us the stigma, discrimination, and mental stress they go through, not to mention the side effects of treatment.
    • Need to address discrimination: While TB can affect people of any class, religion, ethnicity, gender, and socioeconomic status, it disproportionately affects the most marginalized in society, including children, the urban poor, prisoners, and people living with HIV/AIDS. It is needed to address that disease has gone beyond being a health crisis alone.

    How technology can be tapped to address these challenges?

    • Leveraging technology and innovation: The adoption of AI and digital health solutions for TB diagnosis, adherence, and surveillance can revolutionize the way TB care is delivered and accessed in the country.
    • Working on treatments: The path to TB elimination in India requires a concerted effort to prioritize person-centered care, address social determinants of health, and embrace innovation. By investing in developing better vaccines, we can hope to ultimately eliminate this airborne disease.
      • The System for TB Elimination in the Private Sector (STEPS) has been introduced as a low-cost solution to address gaps in quality care for TB patients accessing the private sector.

    Conclusion: By adopting a holistic and person-centered approach, India can overcome the barriers that stand in the way of TB control and create a healthier future for all its citizens.

    https://www.thehindu.com/opinion/lead/tb-control-in-india-calls-for-person-centred-solutions/article67988183.ece

  • Why has Karnataka banned certain coloring agents?

    Why in the news?

    • Karnataka has become the third state in South India to prohibit the use of specific coloring agents in cotton candy and gobi manchurian due to their identified harmful effects.

    Context-

    • While the Government plans to create awareness among manufacturers, it has also urged consumers to be aware of what they are consuming.
    • The Food Safety and Standards Act, 2006 stipulates a fine of not less than ₹10 lakh and a jail term of a minimum of seven years, extending to life imprisonment, against those using banned chemical substances in food products.

    What did the survey results show?/Key findings from the sample testing

    • Presence of Harmful Chemicals: Laboratory tests revealed the presence of harmful chemicals in many samples collected from the state.
    • Cotton Candy Samples: Out of 25 cotton candy samples collected, 15 were found to be unsafe as they contained added colors, while the remaining 10 were deemed safe as they were made without added colors.
    • Gobi Manchurian Samples: Among the 171 samples of gobi manchurian collected, 107 were declared unsafe due to the presence of added colors, while 64 were considered safe as they did not contain added colors.

    What were the harmful chemicals?

    • Harmful Chemicals: The unsafe samples of cotton candy contained traces of sunset yellow, tartrazine, and rhodamine-b, while unsafe gobi Manchurian samples had tartrazine, sunset yellow, and carmoisine. Rhodamine-b, a suspected carcinogen, is already banned.
    • Restrictions on Tartrazine: Although tartrazine is an approved artificial food color, there are restrictions on its usage. It can only be used in specific packed food items, with prescribed amounts. It cannot be used in freshly prepared food items.
    • Health Concerns: The Food Safety Commissioner emphasized that prolonged consumption of snacks containing artificial colors can lead to severe diseases like cancer, highlighting the importance of the ban in safeguarding public health.

    What are the Penalties?

    • Prohibition on Artificial Colors: Rule 16 of the Food Safety and Standards Act prohibits the use of artificial colors in the preparation of gobi manchurian.
    • Approved Limits for Food Colors: While certain food colors are allowed within approved limits, non-permitted colors like rhodamine-b should not be used in the preparation of cotton candy.
    • Penalties for Offenders: Violators face severe penalties, including cancellation of licenses for commercial activities, hefty fines, and imprisonment. The Food Safety and Standards Act specifies a minimum fine of ₹10 lakh and a jail term of at least seven years, which can extend to life imprisonment, for those found using banned chemical substances in food products.

    Way Forward:

    • Enforcement and Monitoring: Health safety officials will likely conduct random checks to ensure compliance with the ban on harmful chemicals and artificial colors.
    • Public Awareness Campaigns: The government will continue its efforts to raise awareness among manufacturers and consumers regarding the risks associated with harmful chemicals and artificial colors in food products.
    • Regulatory Review: There might be a review of existing regulations and standards related to food safety to further strengthen controls and ensure comprehensive coverage of potentially risky food items beyond gobi manchurian, such as kebabs, that may use coloring agents.
    • Collaboration with Stakeholders: Collaboration between government authorities, food manufacturers, and other stakeholders in the food industry will be crucial to implement and enforce the ban effectively. This may include consultations, partnerships, and dialogues to address challenges and ensure compliance with regulations.

    Conclusion: Karnataka banned certain coloring agents in response to findings of harmful chemicals in food samples. Strict penalties and enforcement measures are in place, alongside awareness campaigns and collaboration with stakeholders to ensure compliance and safeguard public health.

  • Understanding dialysis outcome patterns in India through a nationwide study 

    Why in the News? 

    Recently, there are some findings from a nationwide private haemodialysis network’, the Lancet Regional Health-Southeast Asia, on the survival of patients receiving haemodialysis in India

    Context:

    • India has amongst the highest number of patients receiving chronic dialysis, globally estimated at around 1,75,000 people in 2018. Daily, the number of patients on dialysis has been increasing.
    • The launch of the National Dialysis Service in 2016 to improve access, and ongoing efforts to develop affordable dialysis systems, are all underlined by the rising incidence of end-stage renal disease in the country.

    What is Hemodialysis?

    A machine filters wastes, salts and fluid from your blood when your kidneys are no longer healthy enough to do this work adequately.


    Key Highlights as per study:

    • Survival with Centre- and Patient-Level: The study found that both centre- and patient-level characteristics are associated with survival rates among patients undergoing haemodialysis.
    • Unexplained Variation Between Centres: Despite considering various centre-based characteristics, there remained unexplained variations in survival rates between dialysis centres across India. This suggests that factors beyond those accounted for in the study may influence patient outcomes.
    • Large Sample Size: The study included a substantial sample size of over 23,600 patients undergoing haemodialysis at any centre in the NephroPlus network between April 2014 and June 2019. This large sample size enhances the robustness of the study’s findings.
    • Primary Outcome: The primary outcome of the study was all-cause mortality, measured from 90 days after patients joined a center. This outcome measure provides valuable insights into patient survival rates over time following the initiation of haemodialysis treatment.
    • Consideration of Individual-Level Variables: The study accounted for various individual-level variables such as sex, smoking status, medical history (e.g., diabetes, heart disease, hypertension, hepatitis B, hepatitis C), education level, monthly household income, dialysis frequency, and vascular access. These variables offer comprehensive insights into patient characteristics and their impact on survival rates.
    • Evaluation of Centre-Level Variables: Centre-level variables, including the frequency of nephrologist visits, number of beds, number of staff, and number of patients, were also considered. These variables help assess the influence of center resources and practices on patient outcomes.

    What were the measuring differences?

    • Limited Data: The only significant study conducted previously in Andhra Pradesh used claims data from a publicly-funded insurance scheme between 2008 and 2012. It included 13,118 beneficiaries and reported a 10.2% mortality rate within six months of starting hemodialysis.
    • Absence of Centre-Level Effects: The previous study did not consider center-level effects on survival, limiting the understanding of differences in survival rates between dialysis centers, as observed in other countries.
    • Gaps in Understanding: Major gaps existed in understanding dialysis outcome patterns in India due to the absence of comprehensive studies, hindering efforts to improve patient care.
    • Lack of National Benchmark: There was no established national benchmark for survival rates among patients undergoing dialysis in India at the time of the study.
    • Need for Further Research: The study highlighted the importance of conducting more extensive research to fill the gaps in knowledge and establish benchmarks for dialysis outcomes in India.

    What is the recent issue related to the Mortality rate? 

      • Administrative challenges associated with Mortality:
        • Impact of Centre-Level Factors: Including center-level factors such as staffing, care processes, and patient volume in the analysis reduced the variability in survival rates across dialysis centers by 31%. This suggests that center-level characteristics play a significant role in influencing patient outcomes and survival rates.
        • Survival Range: After adjusting for multi-level factors, the estimated 180-day survival among patients undergoing hemodialysis ranged between 83% and 97%. This variability indicates differences in survival outcomes across dialysis centers in India.
      • Urban-Rural Divide: Patients attending rural dialysis centers experienced a 32% higher mortality rate compared to those at urban centers. This disparity underscores the unique challenges faced by rural healthcare facilities in providing hemodialysis services.
    • Patient Characteristics Associated with Mortality:
      • Catheter-Based Vascular Access: Patients using catheter-based vascular access had a higher mortality rate compared to those using arteriovenous fistula or graft access.
      • Financial Support: Patients receiving financial support for dialysis treatment through government panel schemes or private insurance had a lower mortality rate compared to those paying out-of-pocket.
      • Dialysis Vintage: There was an inverse relationship between mortality rate and dialysis vintage, with patients receiving dialysis for at least a year before joining a center experiencing a 17% lower mortality rate than those starting dialysis less than 30 days before joining.
      • Presence of Diabetes: The presence of diabetes was associated with a higher mortality rate among hemodialysis patients.

    Way Forward:

    • Establishment of National Benchmark: The study proposes the first national benchmark for survival among dialysis patients in India. This benchmark will serve as a reference point for evaluating the quality of care and outcomes across dialysis centres in the country.
    • Ongoing Quality Improvement Programs: As dialysis access continues to expand in India, ongoing quality improvement programs are crucial for ensuring that patients receive the best possible care and experience optimal outcomes at the point of care.
    • Collaborative Quality Improvement System: The authors emphasize the need for a collaborative quality improvement system across the country to address the increasing demand for dialysis services. This system should involve stakeholders at various levels of healthcare delivery to enhance standards of care and patient outcomes.
    • Understanding Multilevel Effects: It is essential to understand the multilevel effects of both centre- and patient-level characteristics on dialysis outcomes. Establishing national standards for dialysis outcomes in India requires comprehensive insights into these factors to drive improvements in care delivery.
    • Comparison and Monitoring: Establishing national benchmarks enables comparison and monitoring of dialysis centres’ performances over time. This approach facilitates the identification of variations in practice patterns and outcomes, paving the way for targeted interventions and improvements in healthcare delivery.

    Conclusion: The nationwide study on haemodialysis outcomes in India highlights disparities and the need for standardized care. Establishing national benchmarks, ongoing quality improvement, and collaborative efforts are essential for enhancing dialysis care and patient outcomes.

    Mains PYQ-

    Q- Public health system has limitations in providing universal health coverage. Do you think that private sector can help in bridging the gap? What other viable alternatives do you suggest? (UPSC IAS/2015)

  • [pib] ULLAS Initiative

    Why in the news

    • The Department of School Education and Literacy (DoSEL), Ministry of Education recently conducted the Foundational Literacy and Numeracy Assessment Test (FLNAT), under the ULLAS – Nav Bharat Saaksharta Karyakram Initiative.

    Foundational Literacy and Numeracy Assessment Test (FLNAT)


    • FLNAT is a nationwide assessment test conducted as part of the ULLAS initiative.
    • It aims to evaluate the foundational literacy and numeracy skills of registered non-literate learners aged 15 and above.
    • The assessment covers three aspects – Reading, Writing, and Numeracy – and is conducted in all districts of participating states/UTs.
    • The test plays a crucial role in assessing the impact of teaching-learning sessions conducted under the ULLAS program and promoting literacy and numeracy skills among citizens.
    • It is conducted in the regional language of the learners, aligning with the NEP 2020’s emphasis on multilingualism
    • Qualifying learners receive a certificate from the National Institute of Open Schooling (NIOS).

     What is ULLAS Initiative?

    • ULLAS stands for Understanding Lifelong Learning for All in Society.
    • It seeks to advance lifelong learning and bridge literacy gaps among individuals aged 15 and above.
    • The program aims to equip citizens with fundamental knowledge and skills essential for personal and national development.
    • The ULLAS User-Friendly Mobile Application serves as a digital platform providing access to a wide range of learning resources via the DIKSHA portal.

    Key Features of ULLAS

    1. Emphasizes continuous learning across all stages of life.
    2. Cultivates a culture of knowledge-sharing and individual growth.
    3. Provides participants with digital literacy skills.
    4. Promotes awareness and empowerment in financial matters.
    5. Imparts vital life skills such as legal literacy and digital competence.
    6. Enhances citizenship awareness and empowerment.
    7. Grants school/university credits to student volunteers.
    8. Offers recognition through certificates, letters of appreciation, and felicitation ceremonies.

    PYQ:

    Consider the following statements:

    1. As per the Right to Education (RTE) Act, to be eligible for appointment as a teacher in a State, a person would be required to possess the minimum qualification laid down by the concerned State Council of Teacher Education.
    2. As per the RTE Act, for teaching primary classes, a candidate is required to pass a Teacher Eligibility Test conducted in accordance with the National Council of Teacher Education guidelines.
    3. In India, more than 90% of teacher -5 education institutions are directly under the State Governments.

    Which of the statements given above is/are correct?  (2018)

    1. 1 and 2
    2. 2 only
    3. 1 and 3
    4. 3 only

    Practice MCQ:

    1. Consider the following statements about the ULLAS Initiative:
    2. It focuses on Foundational Literacy.
    3. Individuals aged 15 and above are eligible under this initiative.

    Which of the given statements is/are correct?

    1. Only 1
    2. Only 2
    3. Both 1 and 2
    4. Neither 1 nor 2
  • Lyme Disease reported in Ernakulam

    In the news

    • A suspected case of Lyme disease caused by the bite of a tick carrying borrelia bacteria has been reported from Koovapady in Ernakulam district.

    What is Lyme Disease?

    • According to the Centers for Disease Control and Prevention (CDC), Lyme is transmitted to humans through the bite of infected blacklegged ticks.
    • Typical symptoms include fever, headache, fatigue, and a characteristic skin rash called erythema migrans.
    • If left untreated, infection can spread to joints, the heart, and the nervous system.

    Symptoms of Lyme Disease

    Symptoms of Lyme disease depend on the stage of the condition.

    (1) Stage 1

    • The early symptoms of Lyme disease begin to appear within 3 to 30 days after a tick bite.
    • In this stage, the disease has a limited set of symptoms that includes rash, fever, headache, muscle aches etc. and hence is called early localised disease.

    (2) Stage 2

    • Stage 2 is often more serious and widespread. It is called early disseminated disease.
    • Symptoms include more rashes on other parts of the body, neck pain or stiffness, muscle weakness on one or both sides of the face etc.

    (3) Stage 3

    • In the United States, the most common condition of this stage is arthritis in large joints, particularly the knees.
    • Pain, swelling or stiffness may last for a long time. Or the symptoms may come and go.
    • Stage 3 symptoms usually begin 2 to 12 months after a tick bite.


    Try this PYQ from CSE Prelims 2016:

    Which of the following statements is/are correct? 

    Viruses can infect

    1. bacteria
    2. fungi
    3. plants

    Select the correct answer using the code given below. 

    (a) 1 and 2 only

    (b) 3 only

    (c) 1 and 3 only

    (d) 1, 2 and 3


    [wpdiscuz-feedback id=”p1no71giat” question=”Please leave a feedback on this” opened=”1″]Post your answers here.[/wpdiscuz-feedback]

  • Gendered Challenges in TB Care    

    In the news: Case Study

    • The intersection of gender norms, economic instability, and homelessness presents unique challenges in accessing tuberculosis (TB) care for women like Reshma.
    • Amidst systemic inequities and societal biases, their journey through diagnosis, treatment, and recovery is often fraught with obstacles.
    • A recent study sheds light on the nuanced experiences of homeless women grappling with TB, urging a reevaluation of existing healthcare frameworks.

    Gendered Lens on TB Care

    • Reshma’s Story: Reshma, a homeless woman from Jaipur, embodies the complex narratives surrounding TB care. Her journey, marked by societal abandonment and inadequate healthcare, epitomizes the challenges faced by homeless women battling TB.
    • Gender Norms and Diagnosis: Patriarchal norms influence the accuracy and timeliness of TB diagnosis for women, impacting their access to healthcare facilities and adherence to treatment regimens.
    • Impact of Economic Precarity: Economic instability exacerbates the vulnerability of homeless women, hindering their ability to navigate TB care pathways effectively.

    Data Insights and Inequities

    • Study Findings: A recent survey in Jaipur highlighted the prevalence of TB among the homeless population, underscoring the dire conditions that facilitate TB transmission.
    • Gender Disparities: Homeless women, like Reshma, bear a disproportionate burden of TB infections, revealing systemic gender inequities within TB care systems.

    Barriers to Access and Treatment

    • Documentation Challenges: Lack of identity proof and access to banking services impedes homeless women’s eligibility for government-sponsored TB care Initiatives, such as the Nikshay Poshan Yojana and Nikshay Mitra.
    • Stigma and Social Dynamics: Societal stigma surrounding TB, coupled with patriarchal control over finances, further marginalizes homeless women, hindering their access to nutritional support and treatment adherence.

    Navigating Diagnosis and Care

    • Diagnostic Delays: Vague symptoms and logistical barriers contribute to delayed TB diagnosis among homeless women, prolonging their suffering and increasing the risk of disease progression.
    • Treatment Adherence: Mobility constraints and medication shortages undermine treatment adherence among homeless women, necessitating tailored interventions to address their unique needs.

    Way Forward

    • Inclusive Healthcare Policies: Recognizing the intersectionality of homelessness and gender within TB care, policymakers must prioritize the rights and well-being of homeless women in national TB eradication initiatives.
    • Investment in Care Ecosystems: A comprehensive approach to TB care for homeless women requires increased investment in counselling, tracking, and support services, acknowledging the heightened challenges they face in accessing and adhering to treatment protocols.

    Conclusion

    • Addressing the multifaceted challenges faced by homeless women in accessing TB care demands a concerted effort to dismantle gender biases, mitigate economic disparities, and foster inclusive healthcare ecosystems.
    • By prioritizing equity and empowerment, policymakers can pave the way for a more just and effective TB care paradigm for all individuals, regardless of their socioeconomic status or gender identity.
  • Children’s Vulnerability to Skincare Products

    In the news

    • With the increasing trend of children’s interest in skincare products, concerns have been raised regarding their safety and long-term impact on children’s health.
    • Influenced by social media and marketing, parents are seeking skincare routines for their children, often overlooking potential risks.

    In this article, we explore the implications of early skincare practices on children and the necessity for regulatory measures to ensure their well-being.

    Risks Associated with Children’s Skincare Products

    • Vulnerability to Harm: Children’s skin is thinner, more delicate, and less developed than adults, making them more susceptible to adverse reactions from skincare products.
    • Exposure to Toxicants: Behavioral patterns like hand-to-mouth activity increase the risk of ingesting harmful chemicals present in skincare products, posing health hazards.
    • Biological Susceptibility: Rapid growth rate, developing tissues, and immature immune systems make children biologically more vulnerable to the toxicants present in skincare products.

    Insights from Research

    • Usage Patterns: Research indicates that up to 70% of children in the U.S. have used children’s makeup and body products, highlighting the widespread exposure to skincare products among children.
    • Health Risks: Studies suggest that children’s prolonged exposure to makeup and body products may lead to adverse health effects due to their developing physiology and behavioural tendencies.
    Toxins in skincare products can pose risks to health due to their potential adverse effects. Some common toxic ingredients found in cosmetics include:

    • Polyacrylamide: Possible acrylamide contamination.
    • PTFE: Possible PFOA contamination.
    • Petrolatum: Possible PAH contamination.
    • Formaldehyde: A known carcinogen.
    • Paraformaldehyde: A type of formaldehyde.
    • Methylene glycol: A form of formaldehyde

    Regulatory Imperatives

    • Medical Concerns: Dermatologists express concern over the unsupervised use of cosmeceuticals by children, emphasizing the potential harm caused by substances like steroids and hydroquinone present in skincare products.
    • Need for Regulation: Regulatory measures are deemed essential to restrict the sale of skincare products containing harmful ingredients and protect children from inappropriate products.

    Psychological Impact

    • Unrealistic Standards: The promotion of flawless complexion as an ideal standard perpetuates unrealistic beauty standards among children, impacting their self-esteem and body image.
    • Ethical Considerations: The ethical implications of targeting young consumers with skincare products, without adequate consideration of their long-term effects, warrant scrutiny and regulation.

    Way Forward

    • Prioritizing Safety: Parents are advised to prioritize safety, simplicity, and skin health when selecting skincare products for their children.
    • Return to Basics: Dermatologists advocate for a return to basic skincare practices, including a healthy diet, proper cleansing, and moisturizing, to maintain children’s skin health.
    • Functional Necessity: For child performers and those exposed to heavy makeup, gentle cleansing and hydration are recommended to counteract the effects of makeup and protect the skin’s integrity.

    Conclusion

    • As the children’s cosmetics market continues to grow, it is imperative to address the risks associated with early skincare practices and implement regulatory measures to safeguard children’s health and well-being.
    • By prioritizing safety, simplicity, and skin health, parents can navigate the skincare maze for their children and foster a healthy relationship with skincare that values function over appearance.
  • Have India’s health centres really ‘collapsed’?

    health centres

    In the news

    • Public health centres in India have long been shrouded in infamy, perceived as symbols of systemic failure.
    • The effectiveness of primary healthcare in India has always been a topic of discussion, with calls for strengthening these services through government commitment to accessibility, affordability, and quality care.

    PYQ from CSE Mains 2021:


    Q. “Besides being a moral imperative of a Welfare State, primary health structure is a necessary precondition for sustainable development.” Analyse.

    Health Centres in India

    • Primary Health Centres (PHCs) also known as Public HCs play a crucial role in providing comprehensive healthcare services to the population.
    • The first PHC in India was established following the proposal of the PHC concept in a paper submitted to the Executive Board of the World Health Organization (WHO) in January 1975.
    • The establishment of PHCs gained further momentum with the International Conference on PHC held in Alma Ata, Kazakhstan in 1978.
    • They are a fundamental component of the healthcare system, with Medical Officers at these centers required to hold an MBBS degree.
    • India boasts a vast public health infrastructure with 23,391 PHCs and 145,894 sub-centers, serving a substantial percentage of the population.
    • PHCs cover a significant portion of outpatient care, including services for non-communicable diseases, maternal health, and child health.

    Importance of Health Centres

    • Foundational Role: Health centres form the backbone of India’s public health system, providing primary care to millions.
    • Access and Affordability: With nearly two lakh centres across the country, they aim to offer accessible and affordable healthcare, particularly in rural areas.
    • Impact on Equity: Effective health centres can mitigate social and health inequities, reducing reliance on costly private healthcare and preventing households from falling into poverty due to healthcare expenses.

    Unveiling the Reality

    • Evidence of Progress: Surveys conducted across five states reveal a pattern of improving quality and utilization of health services over time, albeit at a slow pace.
      1. In Himachal Pradesh, functional health centres serve 83% of the population.
      2. Chhattisgarh has shown a radical expansion in the public provision of healthcare, with increased facilities, medicines, and staff presence.
      3. Bihar lags behind, with dismal quality of health centres and some sub-centres being dormant or non-existent.
    • Policy Interventions: Increased health expenditure, initiatives like the National Rural Health Mission, and state-specific schemes have contributed to incremental improvements.
      1. The share of health expenditure in the Union Budget increased drastically.
      2. The National Health Mission’s share shrank from 69% to 44%, while allocations for the Ayushmann Bharat program and new AIIMS hospitals surged.
      3. COVID-19 led to a sustained increase in patient utilization of public health facilities, indicating growing trust in the system.

    Challenges and Gaps

    • Underutilization: Despite improvements, health centres still face challenges such as high staff absenteeism, limited services, and poor infrastructure.
    • Lacunas: Health workers report irregular flow of funds, lack of facilities like toilets and transport, and inadequate supply of drugs and testing equipment.
    • Social Discrimination: Caste and gender dynamics influence access to and quality of healthcare, perpetuating inequalities. Upper-caste doctors display disparaging attitudes towards marginalized communities, while upper-caste families disrespect Dalit ANMs.
    • Gender Disparities: Women, particularly frontline health workers, play a crucial role in rural health settings but often face neglect and discrimination.

    Way forward

    • Holistic Investment: While progress has been made, it remains patchy, with allocations often prioritizing tertiary healthcare over primary care.
    • Designated allocations: The composition of the healthcare budget has remained stagnant, with minimal increases in the share allocated to primary healthcare.
    • Policy Reform: The paper advocates for substantial support from the central government to enable poorer states to replicate successful initiatives and enhance the role of health centres in public healthcare delivery.

    Conclusion

    • India’s health centres, though fraught with challenges, embody resilience and potential.
    • By addressing systemic gaps and prioritizing primary healthcare, the nation can harness the transformative power of these centres to achieve equitable and accessible healthcare for all.
  • Holistic Progress Card (HPC): Revolutionizing Student Assessment

    Holistic Progress Card

    In the news

    • The traditional report cards of students are undergoing a transformation with the introduction of the Holistic Progress Card (HPC) by the National Council for Educational and Research Training (NCERT).
    • This innovative approach aims to evaluate not just academic performance but also various aspects of a child’s holistic development.

    What is the Holistic Progress Card (HPC)?

    • 360-Degree Evaluation: Departing from the conventional marks or grades-based assessment, the HPC adopts a comprehensive evaluation approach.
    • Student-Centric Assessment: Students are actively engaged in the assessment process through class activities, allowing them to demonstrate diverse skills and competencies.
    • Peer and Self-Assessment: Students participate in evaluating their own and their classmates’ performance, fostering self-awareness and peer collaboration.

    Key Features of the HPC

    • Classes Involved: The HPC was created for the foundational stage (Classes 1 and 2), preparatory stage (Classes 3 to 5), and middle stage (Classes 6 to 8). Efforts are currently underway to develop a similar framework for the secondary stage.
    • Parameters of Evaluation: Besides academics, students are evaluated on self-awareness, relationships, problem-solving, emotional intelligence, and creativity. Students reflect on their progress after each activity by circling statements like “I learned something new,” “I expressed creativity,” or “I helped others.”
    • Method of Evaluation:
      1. Self-Assessment: Included in the HPC for all students from Class 1 to Class 8. In middle school (Classes 6 to 8), students set academic and personal goals with specific timelines at the start of the year. The middle stage HPC also involves an “ambition card” where students list their goals for the year and areas for improvement, along with the skills and habits needed to achieve them.
      2. Parental Involvement: Parents provide feedback on homework completion, classroom engagement, and the child’s ability to balance screen time with extracurricular activities at home, thus connecting home and school.
      3. Peer Evaluation: Students evaluate their classmates’ participation in learning and engagement after each classroom activity.

    Implementation and Adoption

    • Rollout across States: The HPC has been sent to all states and Union Territories, with several already adopting it for Classes 1 to 8.
    • Regional Customization: States have the flexibility to modify the HPC to suit their regional requirements while adhering to the overarching principles.

    Rationale behind the Change

    • Focus on Higher-Order Skills: The shift from rote memorization to higher-order skills evaluation aligns with the objectives of NEP 2020 and NCF SE.
    • Promotion of Holistic Development: The HPC aims to communicate students’ strengths and areas of improvement, fostering self-esteem and self-awareness.

    Benefits and Implications

    • Comprehensive Evaluation: The HPC promotes a holistic assessment approach, encompassing academic achievements and critical skill development.
    • Shift to Formative Assessment: By emphasizing formative assessment, the HPC encourages competency-based evaluation and continuous improvement.
    • Insights for Teachers and Parents: Teachers and parents gain valuable insights into each student’s learning journey, enabling personalized support and guidance.

    Conclusion

    • The introduction of the Holistic Progress Card marks a significant step towards redefining student assessment in India.
    • By prioritizing holistic development and competency-based evaluation, the HPC aims to nurture well-rounded individuals capable of thriving in a rapidly evolving world.
  • A vaccine that prevents six cancers

    Pyq mains

    UPSC IAS/2017

    Stem cell therapy is gaining popularity in India to treat a wide variety of medical conditions including leukaemia, Thalassemia, damaged cornea and several burns. Describe briefly what stem cell therapy is and what advantages it has over other treatments? (10)
    Pyq pre 


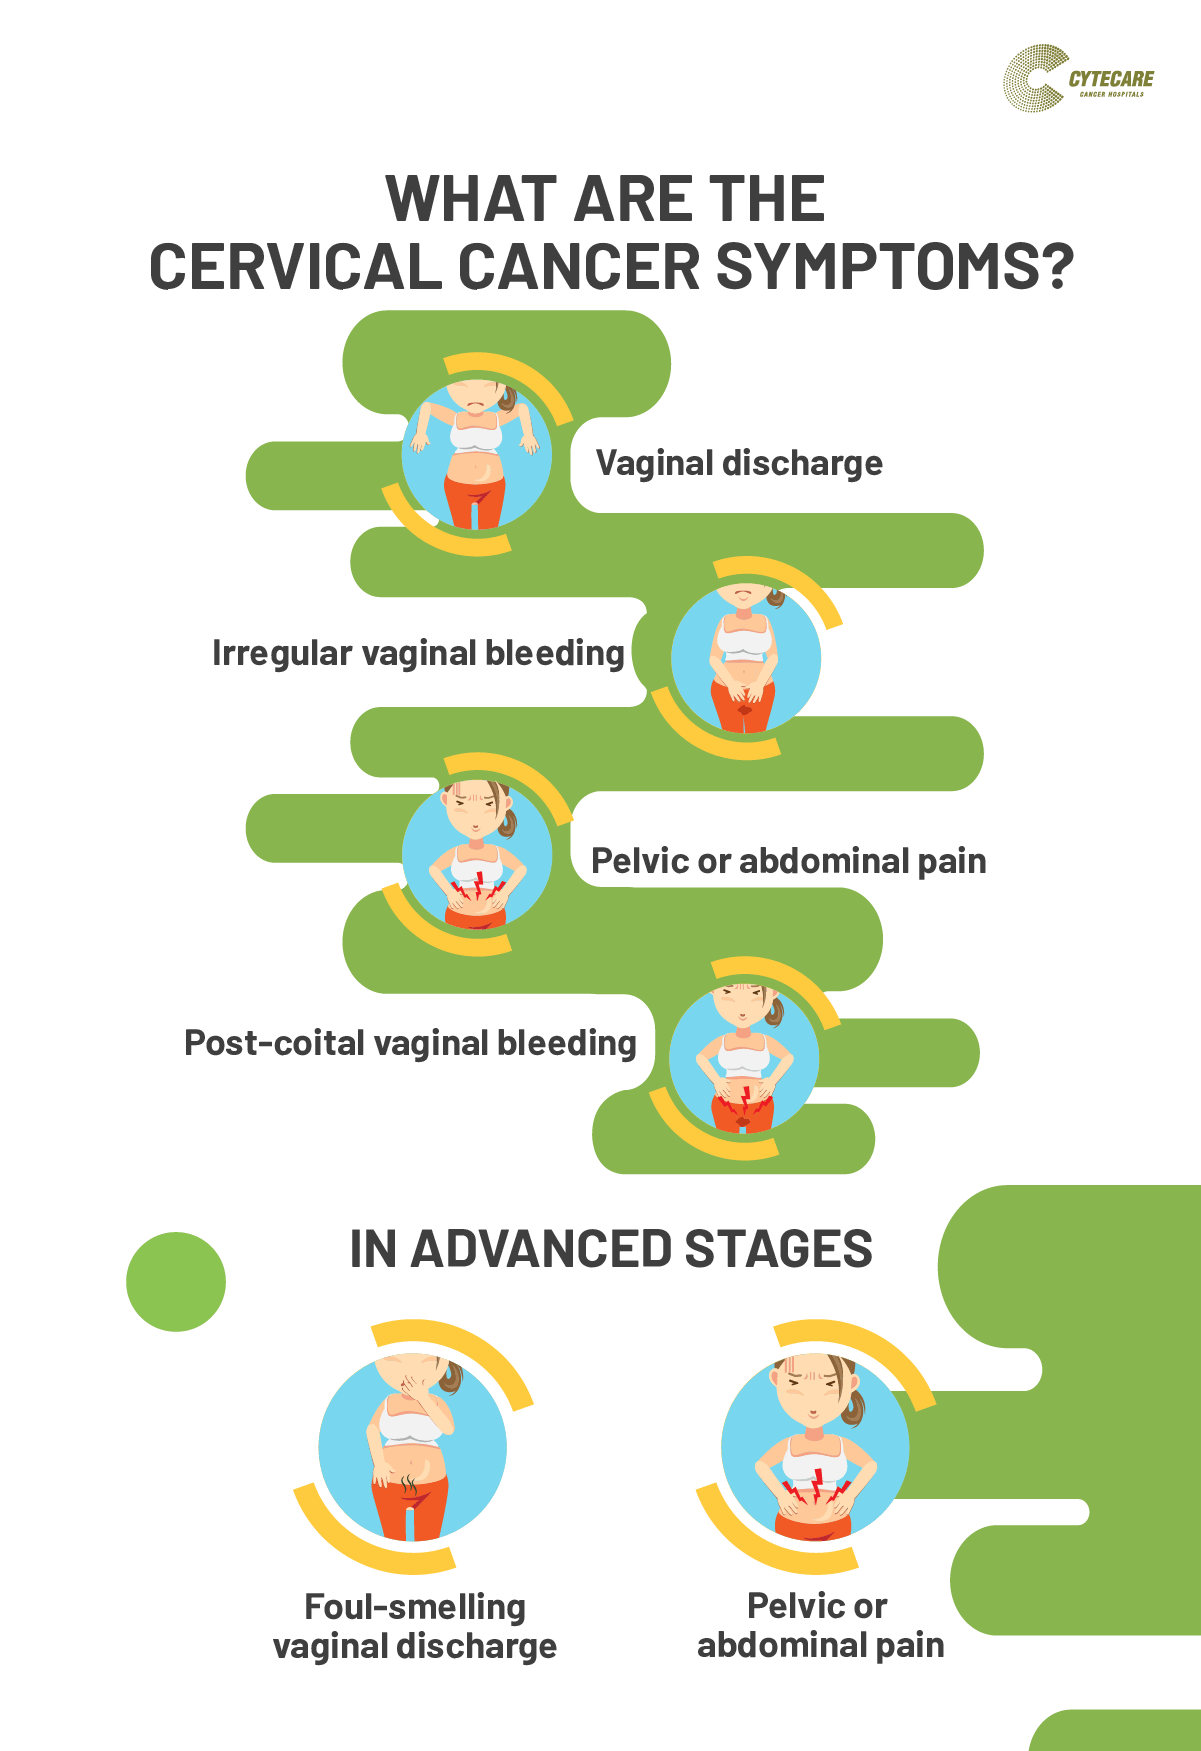
    Cervical Cancer: Symptoms, Diagnosis & Treatment

    Why is it in the News?

    • Cervical cancer prevention, particularly through HPV vaccination, has gained attention recently due to several factors. January was observed as Cervical Cancer Awareness Month, drawing focus to the importance of combating this disease. Additionally, March 4 marked International HPV Awareness Day, further highlighting the significance of addressing HPV-related health issues.

    What is Cervical Cancer?

    • Cervical cancer is a type of cancer that affects the cervix, the lower part of the uterus. It is primarily caused by certain types of the Human Papillomavirus (HPV), which is transmitted through intimate contact.
    • If left untreated, cervical cancer can be life-threatening. It is a significant health concern worldwide, with a particularly high burden in lower- and middle-income countries. In India, cervical cancer is the second most common cancer among women, posing a substantial threat to public health.

    What is Human Papillomavirus (HPV)?

    • Human Papillomavirus (HPV) is a group of viruses that infect the skin and mucous membranes. It’s the most common sexually transmitted infection (STI) worldwide. HPV can cause various health issues, including genital warts and certain types of cancers.

    What Facts are explained in the article?

    • Prevalence and Impact: Cervical cancer claims the lives of over 300,000 women annually worldwide, with a disproportionate burden in lower-income countries.
    • Risk in India: With over 500 million women at risk, cervical cancer is a significant public health concern in India, second only to breast cancer.
    • Role of HPV Vaccination: HPV vaccination is identified as a crucial strategy for preventing cervical cancer. It targets the underlying cause of the disease by protecting against HPV infection.

    Strategies for Prevention of Cervical cancer

    • HPV Vaccination: Implementing widespread HPV vaccination programs, particularly targeting adolescent girls, can significantly reduce the incidence of cervical cancer. Vaccination should ideally occur before the onset of sexual activity to maximize effectiveness.
    • Screening for Precancerous Lesions: Regular screening for precancerous lesions, such as Pap smears or HPV DNA tests, can detect abnormalities early and allow for timely intervention. This is crucial for reducing the incidence of advanced-stage cervical cancer.
    • Education and Awareness: Increasing education and awareness about cervical cancer, HPV infection, and the importance of vaccination and screening are essential. This includes targeting healthcare professionals, policymakers, parents, and adolescents to dispel myths and misconceptions and encourage uptake of preventive measures.

    What are the Challenges?

    • Limited Access: HPV vaccination may not be widely accessible, particularly in lower-resourced communities, and is often available at a significant out-of-pocket cost.
    • Misconceptions Among Physicians: Some physicians underestimate the incidence and risk of cervical cancer, as well as the safety and effectiveness of HPV vaccines. This can lead to hesitancy in recommending vaccination to eligible individuals.
    • Parental Hesitancy: Misinformation and concerns about vaccine safety and efficacy among parents can contribute to hesitancy in vaccinating adolescents against HPV.
    Pap Smears
    Description: A screening procedure for cervical cancer involving collecting cells from the cervix to examine for abnormalities.
    Purpose: To detect precancerous or cancerous changes in cervical cells early for timely intervention and prevention.
    Procedure: Use of a speculum to visualize the cervix and collection of cells with a brush or spatula.
    Timing: Typically performed during routine gynecological exams, starting at age 21 or within 3 years of becoming sexually active.

    Facts about HPV Vaccination:

    • The HPV vaccine is safe and effective in preventing six HPV-related cancers, including cervical, vulvar, anal, vaginal, throat, and cervical cancers.
    • Vaccination is recommended for adolescents starting at age 9 years to maximize its effectiveness.
    • HPV vaccination is an essential component of the immunization schedule recommended by the Indian Academy of Pediatrics (IAP).

    Best Practices for HPV Vaccination and Cervical Cancer Prevention:

    • Effective Communication:
    • Provide clear and accurate information to parents about HPV vaccination.
    • Address concerns and misconceptions to ensure informed decision-making.
    • Timely Vaccination:
    • Recommend HPV vaccination for adolescents starting at age 9.
    • Encourage vaccination before sexual activity begins for maximum effectiveness.
    • Integration into Immunization Programs:
    • Advocate for inclusion in national immunization programs for widespread access.
    • Collaborate with policymakers to ensure equitable vaccine coverage.
    • Promotion of Regular Screening:
    • Emphasize the importance of cervical cancer screening for women over 30.
    • Encourage routine Pap smears or HPV DNA tests for early detection.
    • Physician Education:
    • Provide comprehensive training on HPV vaccination and cervical cancer prevention.
    • Equip healthcare professionals with updated guidelines and communication skills.

    In conclusion, the article emphasizes the importance of proactive measures to prevent cervical cancer, particularly through HPV vaccination and screening. It underscores the role of healthcare professionals, policymakers, and community stakeholders in addressing the challenges and ensuring equitable access to preventive interventions.