💥Mains Ready By December. Smash Mains & Smash PYQ Admissions Open

GS Paper: GS2-13.Issues relating to development and management of Social Sector/Services relating to Health, Education, Human Resources.

  • Annual Status of Education Report (Rural) 2019

    The Annual Status of Education Report (ASER) 2019 (rural) was recently released by NGO Pratham.

    Highlights of the report

    • Only 16% of children in Class 1 in 26 surveyed rural districts can read text at the prescribed level, while almost 40% cannot even recognise letters.
    • Only 41% of these children could recognise two digit numbers.

    Private schools ahead

    • Of six-year olds in Class 1, 41.5% of those in private schools could read words in comparison to only 19% from government schools.
    • Similarly, 28% of those in government schools could do simple addition as against 47% in private schools.
    • This gap is further exacerbated by a gender divide: only 39% of girls aged 6-8 are enrolled in private schools in comparison to almost 48% of boys.
    • The report also found that a classroom could include students from a range of age-groups, skewing towards younger children in government schools.

    Determinants of learning outcomes

    • The ASER report shows that a large number of factors determine the quality of education received at this stage, including the child’s home background, especially the mother’s education level; the type of school, whether anganwadis, government schools or private pre-schools; and the child’s age in Class 1.
    • More than a quarter of Class 1 students in government schools are only 4 or 5 years old, younger than the recommended age.
    • The ASER data shows that these younger children struggle more than others in all skills.
    • Permitting underage children into primary grades puts them at a learning disadvantage which is difficult to overcome,” said the report.

    Role of Mothers

    • Among the key findings of ASER 2019 is that the mother’s education often determines the kind of pre-schooling or schooling that the child gets.
    • The report says that among children in the early years (ages 0-8), those with mothers who had completed eight or fewer years of schooling are more likely to be attending anganwadis or government pre-primary classes.
    • With 75% women in the productive age group not in the workforce, they can be better engaged in their children’s development, learning and school readiness.

    Key suggestions made by the report

    • ASER found that the solution is not to spend longer hours teaching children the 3Rs.
    • Counter-intuitively, the report argues that a focus on cognitive skills rather than subject learning in the early years can make a big difference to basic literacy and numeracy abilities.
    • The survey shows that among Class 1 children who could correctly do none or only one of the tasks requiring cognitive skills, about 14% could read words, while 19% could do single digit addition.
    • However, of those children who could correctly do all three cognitive tasks, 52% could read words, and 63% could solve the addition problem.

    Focus on productive learning

    • ASER data shows that children’s performance on tasks requiring cognitive skills is strongly related to their ability to do early language and numeracy tasks,” says the report.
    • This suggests that focussing on play-based activities that build memory; reasoning and problem-solving abilities are more productive than an early focus on content knowledge.
    • Global research shows that 90% of brain growth occurs by age 5, meaning that the quality of early childhood education has a crucial impact on the development and long-term schooling of a child.
  • [op-ed snap] Taking a holistic approach to dengue

    Context

    The advent of a new tetravalent vaccine against the dengue virus has thrown new light into the evidence-based management of dengue.

    Why the holistic approach is needed

    • Apart from promoting the use of the vaccine, gaining control over dengue will also require a holistic approach that has to include within its ambit vector control and proper case management.
    • Tetravalent vaccine: The vaccine is tetravalent i.e. it provides protection against all the four types of dengue viruses.
      • The vaccine confers about 80% protection to children vaccinated between 4 and 16 years of age without any major side effects.
    • Climatic factors: It is essentially a tropical disease that occurs in the countries around the Equator; hot weather and intermittent rainfall favour the sustenance of Aedes aegypti.
      • Aedes eggs can remain dormant for more than a year and will hatch once they come in contact with water.
    • Risk factors: Urbanisation, poor town planning, and improper sanitation are the major risk factors for the multiplication of such mosquitoes.
      • Aedes eggs can remain dormant for more than a year and will hatch once they come in contact with water.
      • Aedes mosquitoes cannot fly beyond a hundred meters. Hence, keeping the ambiance clean can help prevent their breeding.
      • Further, these mosquitoes bite during the daytime, so keeping the windows shut in the day hours is also useful.

    What needs to be done?

    • Source reduction activities: Activities like preventing water stagnation and using chemical larvicides and adulticides.
      • These chemicals need to be applied in periodic cycles to kill the larvae that remain even after the first spray.
    • Dealing with the manpower shortage: The number of skilled workers available for such measures is low; many posts in government departments remain vacant despite there being a dire public health need.
      • Due to this deficiency of manpower, active surveillance is not being done in India, says the National Vector Borne Disease Control Program.
    • Ending the Under-reporting: Dengue cases are often under-reported due to political reasons and also to avoid spreading panic among the common people. Under-reporting needs to be dealt with.
    • Increasing coordination: There is a lack of coordination between the local bodies and health departments in the delivery of public health measures.
      • A comprehensive mechanism is required to address these issues.
    • Need for epidemiological measures: Any communicable disease needs the epidemiological approach. Singapore uses one successful model of mapping and analysing data on dengue, using Geographical Information System (GIS).
      • The use of GIS involves mapping the streets with dengue cases for vector densities.
    • Emphasis on the WHO guidelines: Fluid management in the body is the cornerstone in the management of severe diseases like dengue hemorrhagic fever and dengue shock syndrome.
      • According to the guidelines, coagulation abnormalities are not due to a reduction in the number of platelets alone.
      • This is why the WHO recommends fresh whole blood or packed cell transfusion in the event of bleeding.
    • Caution in using alternative medicine drugs: Modern medicine is not against any complementary medicine; when such a medicine is approved after rigorous testing.
      • However, in the absence of evidence, the efficacy of such medicines remains in the realm of belief instead of science.
      • So, medicines like Nilavembu kudineer and papaya leaf extract are only belief based.

    Conclusion

    The communicable nature of Dengue and its asymptomatic nature requires the holistic approach to successfully tackle the disease.


  • [op-ed snap] Children of lesser gods

    Context

    The deaths of nearly 200 children in Kota, from largely preventable diseases, lays bare the condition of the healthcare system in India.

    Where does India stand?

    • According to UNICEF’s ‘State of World’s Children 2019’ report, India reported the maximum number of deaths of children under five in the world in 2018.
    • 8,82,000 children under five died that year.
    • That means around 2,416 deaths per day.
    • The death of children due to largely-preventable illnesses is a matter of serious concern and calls for urgent introspection.

    Factors that govern child health

    • Most of the children who died in Gorakhpur, Muzaffarpur and Kota belong to the lowest strata of the society.
    • It won’t be wrong to conclude that they were victims of structural violence.
    • This structural violence is unleashed through a multitude of social, political and economic factors apathy of healthcare professionals, poor health services/infrastructure
    • And low rates of female literacy, economic inequality, the rigid caste system, social apartheid, lack of political will and patriarchy play role.
    • As a society, we have stopped looking at the deaths of our citizens through the prism of compassion and concern.
    • Structural violence influences the nature and distribution of extreme suffering.

    What is being done in the wrong way?

    • The government is considering the takeover of 750 district hospitals by private medical colleges through a public-private partnership (PPP) model.
    • This, despite ample evidence about the failure of the model in the country’s healthcare system.
    • Nobel laureate Kenneth Arrow demonstrated that profit and private involvement in healthcare lead to an erosion of trust.
    • An Individual’s demand for medical services is irregular and unpredictable, the involvement of a private market model for such services can be disastrous.
    • The U.S.’s experiences in the PPP model in healthcare have shone a light on the deficits in transparency and highlighted the lack of care of vulnerable groups.

    Conclusion

    • What urgently a sincere engagement by the state in matters concerning peoples’ health.
    • We need to question the government’s priorities in a country where nearly a million children die every year
  • [op-ed snap] Horror in Kota

    Context

    Death of 100 children in the month of December at a Government Hospital in Kota highlights the state of the public health system in India.

    Public health as a political agenda

    • After the incident of a large number of children in such a short span, Rajasthan CM appealed not to politicise the issue.
    • But it is high time the issue is in fact politicised.
    • The issue of public health needs to be pushed at the top of the political agenda.
    • Citizens must hold political parties accountable for the state of healthcare in the country.

    Poor infrastructure

    • Until the number of deaths crosses a certain threshold the poor state of infrastructure fails to attract the attention of the authorities.
    • This hospital came to light like Gorakhpur Medical college where scores of children had died only after media reports of 963 child deaths.

    Conclusion

    Every single death in a hospital ought to be seen as a failure that needs to be addressed urgently. For that, the government needs to make public health a priority.

  • [op-ed snap]Eradication of TB by 2025

    At the End TB summit, 2018 the prime minister of India made a bold commitment to end tuberculosis by 2025-five years ahead of the global target. Which is possible to achieve if the efforts are put at the level it was done in case of polio.

    The toll taken by TB

    • Despite the disease being fully curable, people still die from it.
    • TB usually affects people in their most productive years and drives families into debt.
    • It has a direct link to human suffering, discrimination and also poverty.
    • Due to its infectious spread, it directly affects our economic growth as well.
    • With resilience, sufficient investment, innovative approaches and strategies and the participation of all stakeholders, TB can be defeated.

    First Step- Awareness

    • The first step is the creation of awareness and empowering of communities.
    • TB affects millions, yet very few know enough about it.
    • Multilingual, multi-stakeholder awareness effort to ensure that all Indians knows about the challenges of TB and where to seek treatment is required.
    • With the expansion of the media and evolving technology, it is possible to reach everyone with the right information.

    Second Step- Access to diagnosis and treatment

    • Ensuring that every Indian get access to correct diagnosis and treatment for TB, regardless of their ability to pay for it is the second step.
    • To do so, working with the private sector is necessary as was done in the case of polio.
    • There are numerous innovative private-sector programmes and partnership schemes for TB.

    Role of  Private sector

    • Recently launched programmes for doctors and labs offer the private sector various incentives.
    • Even today, about half a million TB cases go unnotified, especially those seeking care in the private sector.
    • Those cases need to be tracked and ensured that everyone in the need of treatment and care gets it.
    • Organisations like Indian Medical Association and Indian Academy of Paediatrics are working with the private sector to ensure patient-centric care as per “Standards of TB Care in India” (STCI).

    Drug-resistant TB

    • A key challenge is building a forward-looking plan to address and control drug resistance.
    • Drug-resistant TB is a man-made menace that is a major roadblock in a fight against TB.
    • Every TB patient must be tested for drug resistance at the first point of care, whether in the public or private sector, to rule out any drug resistance.

    Efforts by the government

    • Nikshay Poshan Yojana -in which TB patients receive Rs 500 every month while on treatment was launched.
    • Nikshay Poshan Yojana ensure that the patients have economic support and nutrition during the required period.
    • ‘TB Harega Desh Jeetega Campaign’ was launched to accelerate the efforts to end TB by 2025.
    • The campaign aims to initiate preventive and promotive health approaches.
    • By applying “multi-sectoral and community-led” approach, the government is building a national movement to end TB by 2025.
    • Resource allocation towards the TB Elimination Programme has been increased by four-fold.
    • Sincere efforts need to be made to make our health systems more accessible and reliable.
    • It also required to ensure that those seeking care trust the healthcare system and get the appropriate care for completing treatment.
    • There is a need to create more labs, point of care tests, an assured drug pipeline, access to new drugs.
    • The government should also ensure counselling and support for those affected.
    • Every patient who is diagnosed late and does not receive timely treatment continues to infect others.
    • To break this cycle, government machinery at the field level should work with communities and provide free diagnosis and treatment to every affected individual.

    Conclusion

    With all the efforts, planning and resource put in place to eradicate the menace of TB from India, it is possible to achieve the goal by 2025.

  • SATCOM technology

    The Rajasthan government has started using satellite communication technology in a big way to enhance the learning outcome in educational institutions and generate awareness about social welfare schemes while giving priority to the five aspirational districts selected by NITI Aayog in the State.

    SATCOM

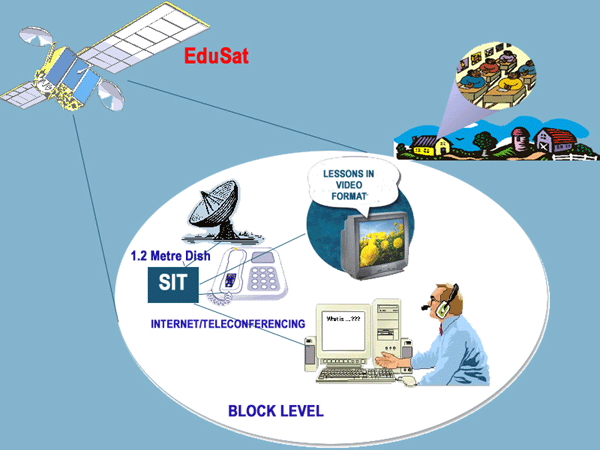
    Rajasthan has taken an initiative to provide the facility of receive only terminals (ROT) and satellite interactive terminals (SIT) for getting the services of subject experts in the government schools and colleges and propagate various schemes in the remote areas with no Internet connectivity.

    What are ROT and SIT?

    • Satellite Interactive Terminal (SIT) is one of the six selected user networks used by CEC-UGC.
    • It is operating independently with their user terminals anywhere in the main land of India.
    • It has one main teaching end along with remote SITs and ROTs.
    • At present, there are over hundred SITs and ROTs under CEC EDUSAT network, installed at various colleges, and Universities across the country.

    Back2Basics

    EDUSAT

    • EDUSAT is the first Indian Satellite built exclusively for serving the educational sector. It was launched in September 2004 by the ISRO.
    • The satellite based distance education system enables virtual classrooms at rural and remote locations across the country.
    • Consortium for Educational Communication (CEC) has started two-way audio-video communication through EDUSAT network from 5th September 2005.
    • ISRO set up a nationwide multi-user educational network in its EDUSAT national Ku – band.
  • 2020 as the “Year of the Nurse and Midwife”

    The World Health Organisation (WHO) has selected the year 2020 as the international “Year of the Nurse and Midwife”.

    Year of the Nurse and Midwife

    • It was decided in the honour of 200th birthday of Florence Nightingale.
    • WHO said that nurses and midwives are the people who devote their lives to caring for children and mothers, looking after senior citizens and giving lifesaving immunizations.
    • The declaration will help to strengthen nursing and midwifery for Universal Health Coverage.
    • The declaration will also help to endorse “The NursingNow!” a three-year campaign (2018-2020) to improve health globally by raising the status of nursing.
  • Mother and Child Health – Immunization Program, BPBB, PMJSY, PMMSY, etc.


    • Aim: To generate awareness and improve efficiency of delivery of welfare services meant for women
    • Launched on 22 January 2015 with an initial corpus of Rs. 100 crore
    • Joint initiative of Ministries of Women & Child Development, Health & Human Resource Development

    Districts Identified

    The three criteria for selection of districts:

    1. Districts below the national average (87 districts/23 states);
    2. Districts above national average but shown declining trend (8 districts/8 states)
    3. Districts above national average and shown increasing trend (5 districts/5 states- selected so that these CSR levels can be maintained and other districts can emulate and learn from their experiences)
    • First Phase:

    100 districts have been identified on the basis of low Child Sex Ratio as per Census 2011 covering all States/UTs as a pilot With at least one district in each state

    • Second Phase

    The scheme has further been expanded to 61 additional districts selected from 11 States/UT having CSR below 918


    Strategies:

    • Implement a sustained Social Mobilization and Communication Campaign to create equal value for the girl child & promote her education
    • Focus on Gender Critical Districts and Cities low on CSR for intensive & integrated action
    • Mobilize & Train Panchayati Raj Institutions/ Urban local bodies/ Grassroot workers as catalysts for social change
    • Ensure service delivery structures/ schemes & programmes are sufficiently responsive to issues Of gender and children’s rights
    • Enable Inter-sectoral and inter-institutional convergence at District/ Block/ Grassroot levels

    Implementation:

    1. Centre: A National Task Force (NTF) headed by Secretary WCD
      State: A State Task Force (STF)
    2. District: District Task Force (DTF) headed by the District Collector/ Deputy Commissioner with representation of concerned departments
    3. Block: A Block Level Committee headed by SDM/ SDO/ BDO
    4. Gram Panchayat/ Municipality: Respective Panchayat Samiti/ Ward Samiti
    5. Village: Village Health Sanitation and Nutrition Committees
    Published with inputs from Swapnil
