💥Mains Ready By December. Smash Mains & Smash PYQ Admissions Open

Subject: Medical and Health Technologies

  • CCTV at medical stores: Why govt wants them, but chemists don’t

    Why in the News

    The Union Health Ministry has proposed mandatory closed circuit television (CCTV) surveillance at medical stores, with recordings retained for three months. The stated purpose is stricter control over prescription medicines, and the draft notification frames it as addressing “unauthorised access to and sale of Schedule H, H1 and X drugs” under the Drugs and Cosmetics Rules, 1945. The measure was first proposed in 2021 to prevent the abuse of drugs by children, and the Drugs Consultative Committee of the Central Drugs Standard Control Organisation (CDSCO) cleared it this year alongside an application based system. The All India Organisation of Chemists and Druggists has objected on cost, on rural power and connectivity, and on patient privacy. What is contested is whether a camera at the counter reaches the behaviour the rule is aimed at, or only records the transaction while leaving the prescription itself unverified.

    What do Schedules H, H1 and X cover?

    1. Schedule H: These medicines cannot be sold without a prescription from a registered medical practitioner, and they include many antibiotics and steroids.
    2. Schedule H1: These are subject to additional record keeping requirements and include certain antibiotics and anti tuberculosis medicines.
    3. Schedule X: This is the more tightly controlled category carrying additional requirements, and it includes some psychotropic medicines.

    Why has the government proposed camera surveillance?

    1. The original trigger: The measure was first proposed in 2021 to prevent the abuse of drugs by children.
    2. Deterrence is the stated mechanism: Round the clock surveillance is intended to create apprehension among medical store owners and pharmacists, so they are not inclined to sell these medicines to children without a prescription.
    3. What the footage is meant to establish: It is meant mainly to verify whether a sale was made to a minor without a prescription, and not all sales can be verified this way.
    4. Retrieval rather than inspection: Routine inspection every three months is difficult, so the data is to be retrieved when a complaint is received.
    5. Paired with a digital system: The Drugs Consultative Committee decided earlier this year to implement the application based system alongside the CCTV plan.

    How common is prescription drug addiction among children?

    1. Opioid use ranks second: Opioid use, covering heroin, opium and pharmaceutical opioids found in strong painkillers, is the second most common form of addiction among children and affects nearly 1.8 per cent of them.
    2. Cannabis leads: Cannabis use affects 19 per cent of children, according to one of the most comprehensive studies of drug use in India, conducted by the All India Institute of Medical Sciences (AIIMS) and published in 2019.
    3. Alcohol and inhalants: Alcohol use affects 1.3 per cent and inhalant use 1.17 per cent of children, and inhalant use is the only form of addiction more common in children than in adults.
    4. Where pharmaceutical opioids sit: Of an estimated 2.3 crore opioid users of all ages, 25 lakh are dependent on pharmaceutical opioids while the largest group of 63 lakh is dependent on heroin.

    What do chemists object to?

    1. Capital cost against turnover: A store may have to spend nearly Rs 1 lakh to put the system in place, which is not viable for a store with daily sales of Rs 5,000 to Rs 10,000.
    2. Rural power and connectivity: Power failures and connectivity problems in rural areas make continuous recording and retention impractical.
    3. Patient privacy: Recording every purchase captures identifiable patients buying identifiable medicines, which the organisation treats as its most important objection.

    Challenges to CCTV surveillance at medical stores

    1. The prescription itself stays unverified: A camera records who bought a medicine and not whether the prescription produced at the counter was genuine or valid. Eg. Most retail prescriptions in India remain handwritten and are not checked against any prescriber registry at the point of sale.
      The Fix: Mandate electronic prescriptions linked to a verified practitioner registry, so validity is checked at dispensing rather than reconstructed from footage afterwards.
    2. Enforcement capacity is the binding constraint: A rule generating three months of footage at every store needs inspectors and laboratories that the drug regulatory system does not have. Eg. The Mashelkar Committee report of 2003 flagged severe shortages of drug inspectors and testing laboratory capacity.
      The Fix: Fill sanctioned drug inspector posts and tie retail licence renewal to a documented compliance record rather than to a periodic fee.
    3. Surveillance without a data protection scaffold: Footage of a patient buying a specific medicine is sensitive personal data, and the draft names a retention period without naming who may access it or for what. Eg. The Digital Personal Data Protection Act, 2023 requires purpose limitation and security safeguards for personal data held by any entity.
      The Fix: Specify in the notification the authority empowered to demand footage, the permitted purpose, and a mandatory access audit log.
    4. Sales migrate to unmonitored channels: A rule that binds the physical counter pushes unprescribed demand toward online and unlicensed sellers that no store camera reaches. Eg. Draft rules to regulate e pharmacies have been under consideration since 2018 without final notification.
      The Fix: Apply the same prescription verification and record keeping obligations to online dispensing before the retail rule takes effect.

    Conclusion

    The proposal is at the draft notification stage and has cleared the Drugs Consultative Committee, so the next step is the final notification and the compliance window given to retailers. The dispute it exposes is narrower than it appears. The state is regulating the place of sale because the prescription behind the sale is not yet auditable, and until it is, a camera records evidence of a transaction rather than evidence of a violation.

    Back2Basics: Central Drugs Standard Control Organisation (CDSCO)

    1. Status: It is India’s national drug regulatory authority, functioning under the Ministry of Health and Family Welfare and headed by the Drugs Controller General of India.
    2. Statutory basis: It operates under the Drugs and Cosmetics Act, 1940 and the Drugs and Cosmetics Rules, 1945.
    3. Functions: It approves new drugs and clinical trials, lays down standards for drugs, and licenses notified categories such as vaccines and blood products.
    4. Drugs Consultative Committee: This is a statutory advisory body under the Act that advises the Centre and the States on securing uniformity in the administration of the Act.

    Matching Previous Year Question

    “[2014, GS3, 12.5 marks] Can overuse and the availability of antibiotics without doctor’s prescription, the contributors to the emergence of drug-resistant diseases in India? What are the available mechanisms for monitoring and control? Critically discuss the various issues involved.”
  • Stem cell therapy for autism only in approved clinical trials: Centre

    Why in the News

    The Union Health Ministry has directed States and Union Territories to ensure that stem cell therapy is offered as standard clinical care only for disease conditions and indications the Ministry has approved, with its use for Autism Spectrum Disorder (ASD) restricted to duly approved clinical trials. The advisory, issued on September 16, follows the Supreme Court’s judgment of January 30, 2026 in Yash Charitable Trust & Ors. v. Union of India & Ors., and reiterates the existing regulatory framework rather than creating a new one. The problem it addresses is a gap between practice and evidence. Stem cell interventions have continued to be offered for autism as commercial clinical services even though an Indian Council of Medical Research (ICMR) review found the available evidence does not support them.

    What does the advisory direct?

    1. Approved indications only: Stem cell therapy may be offered as standard clinical care only for disease conditions and indications approved by the Ministry.
    2. Autism confined to trials: For ASD, therapeutic use of any type of stem cell must remain confined to duly approved clinical trials.
    3. The governing guidelines: Such trials must accord with the National Guidelines for Stem Cell Research, 2017, issued by the ICMR and the Department of Biotechnology.
    4. The commercial bar: Interventions not approved for routine clinical use, including those offered for autism, must not be provided as routine, standard or commercial clinical services.

    What prompted the advisory?

    1. The judgment behind it: The advisory follows the Supreme Court’s January 30, 2026 judgment in Yash Charitable Trust & Ors. v. Union of India & Ors.
    2. Who it was issued to: It was issued to States and Union Territories that have adopted the Clinical Establishments (Registration and Regulation) Act, 2010, which is the statute through which clinical establishments are registered and regulated.
    3. The dissemination duty: States and Union Territories have been asked to pass the Court’s directions down to State and district regulatory authorities, and to government and private clinical establishments involved in stem cell research, treatment, promotion or administration.

    Why does the evidence not support stem cell therapy for autism?

    1. The ICMR finding: An ICMR review concluded that the available evidence does not support stem cell therapy over behavioural and supportive therapies for ASD.
    2. The review’s own recommendation: It recommended that such therapy be restricted to approved clinical trials rather than offered as care.
    3. The practice that continues: Stem cell interventions for autism have continued despite the absence of established evidence supporting them as a standard treatment, which is the conduct the advisory is directed at.

    Challenges to regulating unproven stem cell therapy

    1. Adoption of the governing Act is voluntary: The Clinical Establishments Act applies only in States that have adopted it, so an advisory routed through it does not reach every clinical establishment in the country. Eg. Several large States have their own clinical establishment legislation and have not adopted the central Act.
      The Fix: Route the same directions through each State’s own clinical establishment law, so coverage does not depend on adoption of the central statute.
    2. Guidelines carry no penalty of their own: The National Guidelines for Stem Cell Research, 2017 are guidance rather than statute, so breach is punished only through registration action against the establishment. Eg. Clinics offering unapproved stem cell interventions have continued operating while guidance was in force.
      The Fix: Attach defined penalties for offering unapproved cell based interventions to the rules under the clinical establishment framework.
    3. Advertising reaches patients before regulators do: Families encounter claims for stem cell treatment through direct marketing rather than through referral, so demand is created outside the clinical system. Eg. The Drugs and Magic Remedies (Objectionable Advertisements) Act, 1954 lists conditions for which advertising cures is barred, and enforcement against online claims is thin.
      The Fix: Bring digital advertising of cell based therapies under a prior approval requirement tied to the approved indications list.
    4. Desperation drives cross border and unregulated demand: Where no curative treatment exists, families pursue interventions regardless of the evidence, including outside the country. Eg. Stem cell tourism to jurisdictions with weaker oversight is a documented pattern for neurological conditions.
      The Fix: Publish and maintain a public registry of approved indications and approved trial sites, so families can check a claim before paying for it.

    Conclusion

    The advisory settles the legal position rather than changing it: stem cell therapy for autism is a research question, not a clinical service, and the distinction is now to be enforced through the registration authorities in each State. The instrument’s reach depends on how many States have adopted the Clinical Establishments Act and on whether district regulators act on the directions passed to them. The next measurable step is registration action against establishments that continue to offer the intervention commercially.

    Back2Basics: Clinical Establishments (Registration and Regulation) Act, 2010

    1. Purpose: It provides for the registration and regulation of clinical establishments, with a view to prescribing minimum standards of facilities and services.
    2. Coverage: It applies to all recognised systems of medicine and to both government and private establishments, excluding those run by the armed forces.
    3. How it extends to States: It applies directly in Union Territories and in States that adopt it by resolution, since public health is a State subject.
    4. Institutional structure: It establishes a National Council for Clinical Establishments and requires State Councils and District Registering Authorities to maintain a national register.

    Matching Previous Year Question

    “[2017, GS3, 10] Stem cell therapy is gaining popularity in India to treat a wide variety of medical conditions including Leukaemia, Thalassemia, damaged cornea and several burns. Describe briefly what stem cell therapy is and what advantages it has over other treatments?”

  • ICMR-NICPR validates oral therapy SHetA2 to block HPV’s cancer causing proteins

    Why in News?

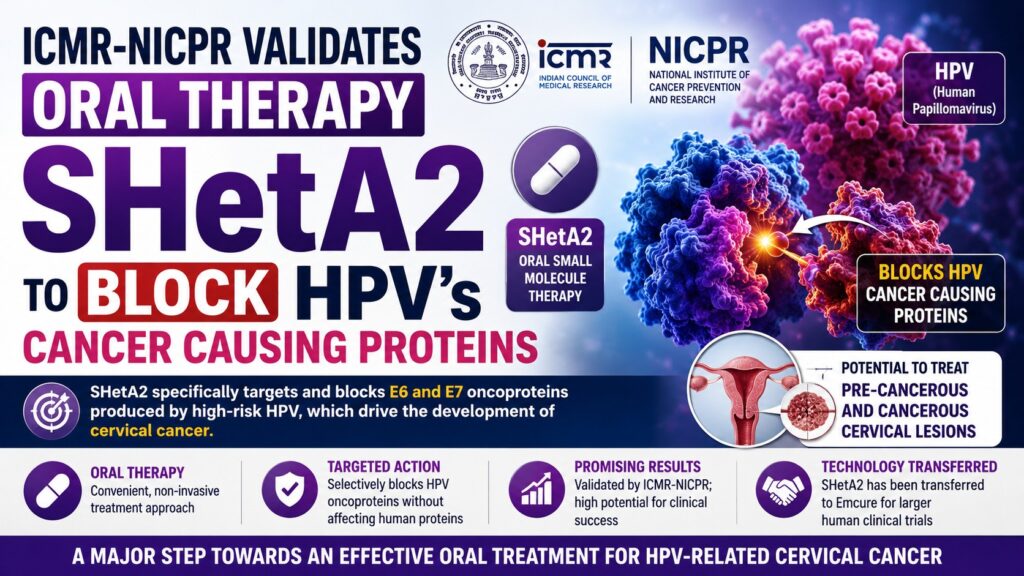
    The Indian Council of Medical Research-National Institute of Cancer Prevention and Research (ICMR-NICPR) has validated an oral small molecule therapy, SHetA2, that blocks Human Papillomavirus (HPV)’s cancer causing proteins, potentially treating pre-cancerous and cancerous cervical lesions. The molecule has been transferred to Emcure for larger human trials.

      Key Highlights

      1. Therapy: SHetA2, an oral small molecule drug.
      2. Mechanism: Blocks HPV oncoproteins (E6 and E7), which drive cervical cancer development.
      3. Target: Designed to treat pre-cancerous (CIN) and cancerous cervical lesions.
      4. Validating body: ICMR-National Institute of Cancer Prevention and Research (ICMR-NICPR).
      5. Next stage: Technology transferred to Emcure for advanced human clinical trials.
      6. Significance: Represents a potential non-surgical, oral treatment for HPV-related cervical disease.

      What is Human Papillomavirus (HPV)?

      1. HPV is a common DNA virus that infects the skin and mucous membranes.
      2. It is transmitted mainly through sexual contact.
      3. Persistent infection with high-risk HPV types, especially HPV-16 and HPV-18, is the leading cause of cervical cancer.
      4. HPV is also associated with cancers of the anus, vulva, vagina, penis and oropharynx.

      How Does SHetA2 Work?

      1. Inhibits the activity of HPV’s E6 and E7 oncoproteins.
      2. Restores the function of tumour suppressor proteins (p53 and Rb), allowing abnormal cells to undergo programmed cell death (apoptosis).
      3. May help prevent progression from pre-cancerous lesions to invasive cervical cancer.

      Significance

      1. Offers a non-invasive oral treatment option for HPV-related cervical lesions.
      2. May reduce the need for surgical procedures in early-stage disease.
      3. Supports India’s efforts to reduce the burden of cervical cancer, one of the most common cancers among women.
      4. Demonstrates the growing role of indigenous biomedical research and public-private collaboration.

      Government Initiatives

      1. National Programme for Prevention and Control of Non-Communicable Diseases (NP-NCD) includes cervical cancer screening.
      2. Introduction of Cervavac, India’s indigenous HPV vaccine, to expand cervical cancer prevention.
      3. Promotion of HPV vaccination, screening and early diagnosis under national health programmes.

      [2021] Consider the following statements:
      1. Adenoviruses have single-stranded DNA genomes whereas retroviruses have double-stranded DNA genomes.
      2. Common cold is sometime caused by an adenovirus whereas AIDS is caused by a retrovirus.
      Which of the statements given above is/are correct?

      [A] 1 only

      [B] 2 only

      [C] Both 1 and 2

      [D] Neither 1 nor 2

    1. GLP-1 Drugs and Their Effects on Skin, Hair & Nails

      Why in News?

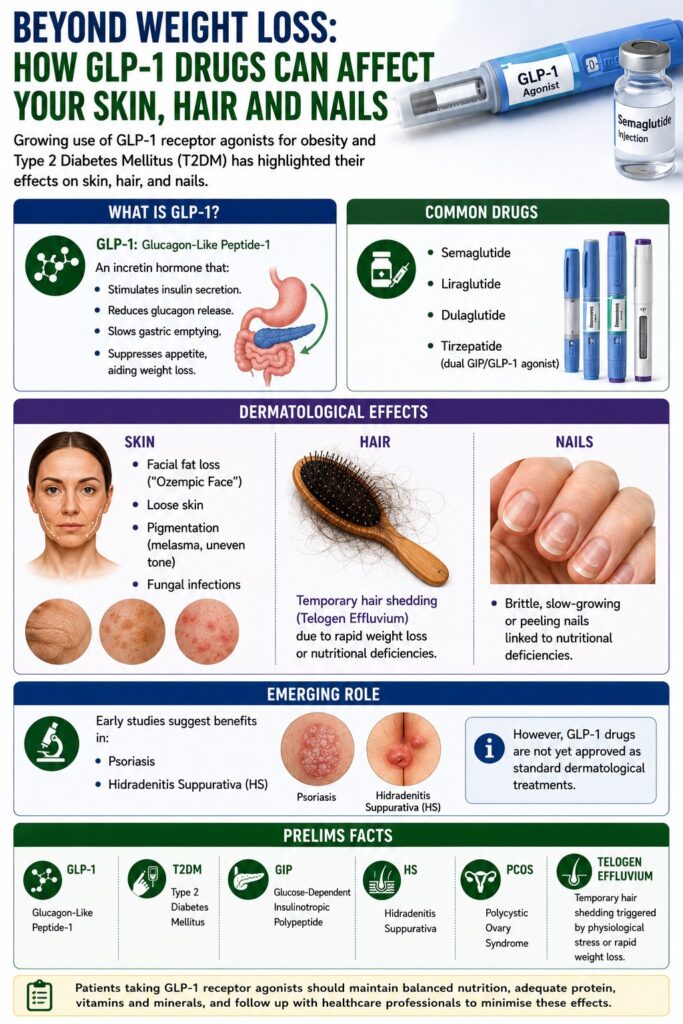
      Growing use of GLP-1 receptor agonists for obesity and Type 2 Diabetes Mellitus (T2DM) has highlighted their effects on skin, hair, and nails.

      What is GLP-1?

      • GLP-1: Glucagon-Like Peptide-1
      • An incretin hormone that stimulates insulin secretion, reduces glucagon release, slows gastric emptying, and Suppresses appetite, aiding weight loss.
      • Common Drugs: Semaglutide, Liraglutide, Dulaglutide, and Tirzepatide (dual GIP/GLP-1 agonist).
      • Emerging Role: Early studies suggest benefits in: Psoriasis and Hidradenitis Suppurativa (HS). However, GLP-1 drugs are not yet approved as standard dermatological treatments.

      Dermatological Effects

      • Skin: Facial fat loss (“Ozempic Face”), loose skin, pigmentation, fungal infections.
      • Hair: Temporary hair shedding (Telogen Effluvium) due to rapid weight loss or nutritional deficiencies.
      • Nails: Brittle, slow-growing or peeling nails linked to nutritional deficiencies.

      Prelims Facts

      • GLP-1: Glucagon-Like Peptide-1
      • T2DM: Type 2 Diabetes Mellitus
      • GIP: Glucose-Dependent Insulinotropic Polypeptide
      • HS: Hidradenitis Suppurativa
      • PCOS: Polycystic Ovary Syndrome
      • Telogen Effluvium: Temporary hair shedding triggered by physiological stress or rapid weight loss.

      [2024] Which one of the following is synthesised in human body that dilates blood vessels and increases blood flow

      [A] Nitric oxide

      [B] Nitrous oxide

      [C] Nitrogen dioxide

      [D] Nitrogen pentoxide

    2. Antibiotics to creams: The perils of combination meds

      Why in the News?

      The government has banned 16 fixed-dose combination (FDC) drugs, including antibiotic and dermatological formulations, for lacking scientific justification. The ban exposes that many combinations survived in the market for years on commercial convenience rather than clinical evidence. This exposed patients to unnecessary risk and worsening antimicrobial resistance.

      What triggered the ban on 16 fixed-dose combination drugs?

      1. Scope of the ban: The government banned 16 FDC drugs, covering antibiotic combinations and dermatological products containing aloe vera and other herbal ingredients.
      2. Stated ground for the ban: The banned products lack scientific justification for their claimed amplified benefit.
      3. Definition of the underlying problem: An FDC is irrational when its ingredients have no scientifically established rationale for being combined in a single product.
      4. Test for rationality: Each component must contribute meaningfully to the intended therapeutic effect, have compatible pharmacological properties, and demonstrate additional clinical benefit compared to using the medicines individually.
      5. Evidentiary gap: In many banned cases, no clinical trial evidence supports the combination.

      Why does a combination drug’s long presence in the market not establish its scientific validity?

      1. Central tension: Longevity in the market does not establish scientific validity.
      2. Case in point: Many banned dermatological combinations contained aloe vera extracts, vitamin E, jojoba oil, olive oil, tea tree oil, and other moisturising or herbal components, sold for years despite lacking evidence.
      3. The real question: Whether combining these ingredients produces a measurable clinical benefit compared with using them individually.
      4. Evidentiary standard: Robust scientific evidence demonstrating superior efficacy is lacking for many such products.
      5. Illustrative failure: Combination creams pairing a steroid and an antifungal give temporary relief from itching and redness because the steroid suppresses the skin’s local immune response, but this same suppression allows the underlying fungal infection to worsen, spread, or become resistant to treatment.
      6. Governance root cause: In the pre-reform period, thousands of FDCs were approved by state licensing authorities without central review, exploiting a regulatory loophole in the Drugs & Cosmetics Act. 

      What do specific banned combinations reveal about irrational drug design?

      1. Amoxicillin + serratiopeptidase: Serratiopeptidase is acid-labile, meaning it degrades in the stomach before reaching the bloodstream.
      2. No demonstrated benefit: No evidence shows that adequate therapeutic concentrations of serratiopeptidase reach infected tissues.
      3. No trial support: No peer-reviewed randomised controlled trial has shown that adding serratiopeptidase improves bacterial clearance, increases cure rates, or reduces the antibiotic dose required.
      4. Norflox TZ (norfloxacin + tinidazole): Tinidazole is pointless for purely bacterial diarrhoea; norfloxacin provides zero benefit for amoebic dysentery. Patients rarely have both infections simultaneously, yet exposure to both drugs unnecessarily promotes bacterial resistance.
      5. Augmentin 625 (amoxicillin + clavulanic acid): Clavulanic acid blocks the enzyme that resistant bacteria use to destroy amoxicillin, but is useless if the infecting bacteria are not resistant.
      6. Guideline recognition: No major treatment guideline currently recommends serratiopeptidase as an antibiotic adjunct for managing infections.

      What does global regulatory practice show about evaluating combination drugs?

      1. United States: All FDCs require a new drug application supported by clinical evidence of superiority or convenience over the individual components.
      2. World Health Organization: The WHO explicitly cautions against irrational FDCs; only combinations on its essential medicines list are treated as evidence-based.
      3. European Union: FDCs undergo full scientific review and can be justified only with supporting clinical data.
      4. India (pre-reform): Thousands of FDCs were approved by state licensing authorities without central review, exploiting a loophole in the Drugs & Cosmetics Act.
      5. India (post-2016): Around 6,000 FDCs were reviewed by a central committee, and bans have been initiated in phases since.

      How do irrational antibiotic combinations contribute to antimicrobial resistance?

      1. Marketing effect: When combinations are marketed as more effective without sufficient evidence, they encourage unnecessary and prolonged antibiotic use.
      2. Exposure pathway: This increases antibiotic exposure in the community and creates selective pressure on bacteria.
      3. Resistance mechanism: Selective pressure allows resistant organisms to survive and multiply.
      4. Policy implication: From a public health perspective, antibiotic use should be as targeted and evidence-based as possible.
      5. Scale of the underlying problem: AMR is a growing public health problem because bacteria, viruses, fungi, and parasites no longer respond to the medicines designed to kill them.

      What risks do patients face from irrational FDCs?

      1. Unnecessary drug exposure: Patients face an increased possibility of adverse effects, drug interactions, and allergic reactions.
      2. Dose inflexibility: Fixed combinations make it difficult for doctors to adjust the dose of individual ingredients to a patient’s needs.
      3. Titration failure: If a doctor wants to increase the dose of one medication, this cannot be done without also increasing the other.
      4. Diagnostic masking: Combination drugs can mask an underlying complication, reducing precision in treatment.

      What should patients, doctors, and pharmacists do now that these products are banned?

      1. Patient understanding: A medicine with multiple ingredients is not necessarily more effective than a targeted treatment.
      2. Preferred alternative: A simpler medicine supported by strong evidence is often the safer and more effective option.
      3. Continuity of care: Patients using banned products should consult their doctor about alternatives; stopping an irrational FDC does not mean stopping treatment.
      4. Doctor’s role: The focus should be on de-escalating patients to rational therapies supported by evidence.
      5. Pharmacist’s role: Pharmacists should track the regulator’s list of banned FDCs, flag irrational prescriptions, and educate patients on available alternatives.
      6. Related caution- vitamins and probiotics with antibiotics: There is no definitive evidence that pairing them with antibiotics is indispensable; probiotics may be advised case-by-case, and vitamins are generally unnecessary for a short antibiotic course except in vulnerable groups.

      Conclusion

      A drug combination’s survival in the market does not establish its scientific validity; irrational FDCs persisted because regulatory review was historically weak, not because evidence supported them. Regulatory decisions on combination drugs must rest on clinical trial evidence and risk-benefit assessment rather than duration of commercial availability. Continuous post-marketing surveillance is needed to identify and withdraw irrational combinations before they further entrench antimicrobial resistance.

      PYQ Relevance

      [UPSC 2013] What do you understand by Fixed Dose Drug Combinations (FDCs)? Discuss their merits and demerits.

      Linkage: The PYQ asks for a direct conceptual and evaluative treatment of FDCs. The article supplies current, case-specific demerits (Norflox TZ, Augmentin 625, serratiopeptidase, dermatological creams) that can update and substantiate this answer.