💥Mains Ready By December. Smash Mains & Smash PYQ Admissions Open

GS Paper: GS2-13.Issues relating to development and management of Social Sector/Services relating to Health, Education, Human Resources.

  • [25th November 2025] Hindu OpED Bridging India’s numeracy gap

    PYQ Relevance
    [UPSC 2020] National Education Policy 2020 is in conformity with the Sustainable Development Goal-4 (2030). It intends to restructure and reorient education system in India. Critically examine the statement.
    Linkage: NEP 2020 aligns with SDG-4 by focusing on equitable, high-quality education and foundational learning. However, implementation gaps and weak learning outcomes, especially in numeracy, limit its SDG-4 impact so far.
    Mentor’s Comment
    India’s learning crisis has silently shifted from illiteracy to numeracy failure. While the National Education Policy (NEP) 2020 and NIPUN Bharat Mission strengthened foundational literacy, recent evidence shows that numeracy continues to stagnate sharply, closing the doors of higher education for millions. This article decodes why numeracy outcomes matter for economic, cognitive, and social mobility, and what a multi-pronged policy roadmap must look like.
    INTRODUCTION
    NEP 2020 identifies Foundational Literacy and Numeracy (FLN) as the cornerstone of future learning, and NIPUN Bharat translated this into classroom action. While literacy outcomes have shown improvement, numeracy remains stubbornly low, particularly in conceptual understanding and real-life application. India is now at a point where foundational literacy success must be expanded to higher-order mathematical learning.
    WHY IN THE NEWS 
    The Annual Status of Education Report (ASER) 2024 shows that while 48.7% of Class 5 students read fluently, only 30.7% can solve a basic division problem, marking an 18% performance gap between literacy and numeracy. No State reports higher numeracy than literacy, highlighting a national trend of mathematics stagnation. Also, nearly 70% of Class 8 students and more than 50% of Class 5 students remain unable to perform basic division, despite classroom-based math instruction. The gap between school learning and real-life mathematical use is widening, closing higher-education opportunities as teens fail to cross the Class 10 board exam numeracy threshold.
    Where does India’s numeracy gap originate?
    1. Hierarchical nature of mathematics: partial understanding in lower grades (e.g., place value) blocks higher concepts such as addition and decimals.
    2. Cumulative error effect: once gaps form, students rarely recover, unlike in language.
    3. Traditional syllabus-driven pedagogy: focuses on advancement, not mastery; students progress without clearing conceptual blocks.
    Why does classroom learning not translate into real-world mathematical ability?
    1. High classroom performance, low life applicability: Evidence from the Abdul Latif Jameel Poverty Action Lab: students who excel in assessments fail to apply math in real-life situations.
    2. Real-world tasks do not transfer to classroom problems: Children able to handle money or shop-related calculations cannot solve textbook problems.
    3. Mismatch in learning environment: Schooling moves faster than the pace of conceptual consolidation.
    What are the consequences of India’s numeracy stagnation?
    1. Academic roadblocks: students struggle in science and mathematics subjects that dominate board exams.
    2. Early exit from education: adolescents leave school before Class 10 due to fear of mathematics.
    3. Reduced human capital formation: failure to master numeracy blocks access to high-skill employment and technical careers.
    Why does Foundational Literacy and Numeracy (FLN) need expansion beyond early grades?
    1. Persistent learning gaps after Grade 3: 70% of Class 5 and more than 50% of Class 8 students cannot divide.
    2. COVID-19 widened numeracy deficits: most Class 3 students reached upper-primary without core math skills.
    3. Transferable higher-grade pedagogy required: FLN-style teaching must be extended to older students.
    What does an effective multi-pronged response look like?
    1. Strengthening middle-grade support: extend FLN interventions to Class 8 to prevent permanent numeracy loss.
    2. Teaching math through everyday life: bills, ratios, fractions, percentages, and measurements.
    3. Child-friendly activity-based pedagogy: aligned with real literacy levels rather than grade-based syllabus.
    4. Embedding numeracy across subjects: problem-solving in science, geography, social sciences.
    CONCLUSION
    India has cracked foundational literacy but not foundational numeracy. The nation stands at a turning point where classroom success must evolve into real-life mathematical competence, ensuring that students not only pass but thrive academically and economically. Extending FLN-style pedagogy to middle-grade stages remains the most urgent policy priority.

  • [24th November 2025] The Hindu OpED: The future of health lies in harmony

    PYQ Relevance

    [UPSC 2019] How is the Government of India protecting traditional knowledge of medicine from patenting by pharmaceutical companies?

    Linkage: Traditional medicine is gaining global traction, so protecting it from patenting and biopiracy is now a core policy priority rather than a cultural concern. As India leads the global traditional medicine agenda, this linkage makes the topic very likely to appear in future UPSC exams under health governance, IPR and soft-power.

    Mentor’s Comment

    The global health landscape is undergoing a paradigm shift. Traditional medicine, once seen as alternative, is now being recognised as a scientific and social asset. With India emerging as a hub of innovation and evidence-based traditional research, and hosting the Second WHO Global Summit on Traditional Medicine, the world is witnessing a renewed focus on health systems rooted in balance, sustainability and technology-enabled well-being.

    INTRODUCTION

    Health, in its original meaning, has always signified harmony, within the human body, and between humans and nature. With modern lifestyles driving chronic diseases, mental strain and ecological imbalance, traditional systems of medicine offer a rediscovered pathway to well-being that integrates mind, body, community, and environment. India, with its rich heritage of Ayurveda, Yoga, Unani, Siddha and Sowa-Rigpa, is repositioning traditional medicine as an engine of science-driven global healthcare transformation.

    WHY IN THE NEWS?

    The Second WHO Global Summit on Traditional Medicine hosted by India marks a watershed moment, for the first time, traditional medicine is being institutionalised globally as a scientific, evidence-backed and sustainable component of public health systems. With around 90% of WHO member-states reporting usage of traditional medicine, and India’s AYUSH market reaching USD 34.3 billion, global health priorities are shifting from reactive sick-care to proactive well-being. The Summit signals the beginning of a new chapter where traditional medicine integrates with modern technologies, data analytics and global governance.

    Why is traditional medicine gaining global significance?

    1. Escalating lifestyle diseases: rising non-communicable diseases demand preventive, holistic models of care.
    2. Fragmented systems failing: reactive, curative-centric models cannot ensure long-term public well-being.
    3. Biodiversity-nutrition-livelihood interlinkages: traditional medicine influences food security, sustainability and livelihoods.
    4. Affordability for LMICs: for billions across low- and middle-income regions, traditional medicine remains first access to healthcare.

    How is traditional medicine evolving from belief to science?

    1. Evidence-based research: WHO emphasises integration supported by data, learning and scientific validation.
    2. Shift from consumer preference to collective responsibility: well-being linked to shared ecosystems and sustainability.
    3. Recognition as a scientific and social asset: elevated at the 2023 WHO Summit in Gandhinagar.
    4. Institutional reforms in India: dedicated AYUSH department at BIS, and global standards under ISO/TC 249/SC 2.

    What is India’s leadership role in global traditional medicine?

    1. WHO Global Traditional Medicine Centre (GTMC) in Jamnagar: a knowledge hub for innovation, analytics and sustainability.
    2. Memorandum of Understanding with WHO: India co-hosts global Summit and participates in shaping global priorities.
    3. Political and scientific commitment: Prime Minister’s focus leads to increasing investments and ecosystem building.
    4. Vision of collective global stewardship: India positions traditional knowledge as shared global heritage.

    How does technology change future pathways of traditional medicine?

    1. Digital health and analytics: enable real-time monitoring, transparency and measurable clinical outcomes.
    2. Sustainability and biodiversity research: bridges traditional practice with ecological protection.
    3. Innovation-led scaling: makes traditional systems compatible with global regulatory and safety frameworks.
    4. Data-driven inclusion: ensures equitable access to health knowledge and solutions.

    How does the Summit reshape global health governance?

    1. Benefit sharing and fair access: ensures equitable utilisation of biological and cultural assets.
    2. Value of local heritage in globalisation: respects indigenous knowledge in global supply chains.
    3. Integration with modern health priorities: aligns traditional medicine with contemporary clinical and public health goals.
    4. Ethical anchoring of future innovation: technology with community-rooted ethics and sustainability.

    CONCLUSION

    The world is moving toward a health model where prevention, sustainability, community participation and science converge. Traditional medicine, empowered by research, technology and equitable access, offers a pathway to resilience against lifestyle diseases and global health inequalities. India’s leadership in steering this transformation reinforces health not as the absence of disease, but as a state of balance between humans and nature.
  • Ultra-Processed Food Epidemic in India

    Why in the news?

    A recent Lancet three-paper series highlights the rapid rise in ultra-processed food (UPF) consumption globally, including India, and its strong link to rising obesity, diabetes, cardiovascular diseases, and premature mortality. The case of an 18-year-old Indian youth with obesity and early-onset metabolic disorders illustrates the growing public health crisis.

    What are Ultra-Processed Foods?

    According to the NOVA classification, ultra-processed foods are:

    • Industrial formulations with multiple chemical and cosmetic ingredients
    • Made using high-fructose corn syrup, hydrogenated oils, flavour enhancers, emulsifiers, preservatives, colours
    • Designed for long shelf life, hyper-palatable taste and convenience
      Examples: Soft drinks, chips, packaged noodles, biscuits, sugary beverages, chocolates, breakfast cereals, frozen pizzas, ready-to-heat meals, chicken nuggets, processed meats.

    Difference from Processed Foods:
    Processed = minimal changes (washing, canning, cooking).
    Ultra-processed = heavy industrial formulations, low nutrients, high calories.

    Note: NOVA is a food classification system developed by the University of São Paulo (Brazil) that categorises foods based on the extent and purpose of industrial processing, not nutrients.

    India’s UPF Consumption – Why It’s a Concern?

    • Huge surge in consumption: Retail sales of UPFs in India jumped from USD 0.9 billion (2006) → USD 38 billion (2019) (approx. 40-fold increase).
    • Rising NCD (Non-Communicable Diseases) burden: As per ICMR–INDIAB (2023): Obesity: 28.6%, Diabetes: 11.4%, Prediabetes: 15.3%, Abdominal obesity: 39.5% and Childhood obesity rising: 2.1% → 3.4% (NFHS).
    A company marketing food products advertises that its items do not contain trans-fats. What does this campaign signify to the customers? (2011)

    1. The food products are not made out of hydrogenated oils. 

    2. The food products are not made out of animal fats/oils. 

    3. The oils used are not likely to damage the cardiovascular health of the consumers. 

    Select the correct answer using the code given below: 

    (a) 1 only (b) 2 and 3 only (c) 1 and 3 only (d) 1, 2 and 3

  • Tuberculosis incidence falling in India by 21% a year: WHO report

    Why in the News?

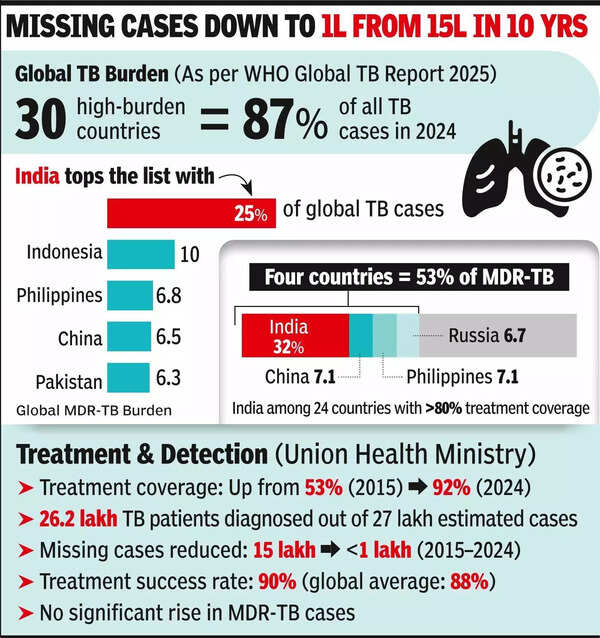
    The World Health Organization’s Global TB Report 2025 says India’s TB incidence dropped 21% from 237 to 187 per lakh between 2015 and 2024, almost twice the global decline rate of 12%.

    Tuberculosis incidence falling in India by 21% a year: WHO report

    About Global TB Report 2025:

    • Publisher: Released by the World Health Organization (WHO) in November 2025.
    • India’s TB Incidence Decline: Fell 21 percent from 237 to 187 cases per lakh (2015–2024), nearly double the global decline of 12 percent.
    • Treatment Coverage: Reached 92 percent, with 26 lakh cases diagnosed in 2024.
    • Mortality Reduction: Dropped from 28 to 21 deaths per lakh between 2015–2024.
    • Key Drivers: Community-based screening, molecular diagnostics (CBNAAT / Truenat), Ni-kshay digital tracking, and TB Mukt Bharat Abhiyan.

    About Tuberculosis (TB):

    • What is it: Bacterial disease caused by Mycobacterium tuberculosis mainly affecting the lungs; spreads through air via coughing/sneezing.
    • Types of TB:
      • Pulmonary TB: Affects lungs, highly contagious.
      • Extrapulmonary TB: Affects organs like spine, kidneys, brain, or lymph nodes.
      • Latent TB: Dormant infection, asymptomatic but may reactivate.
      • Active TB: Symptomatic and infectious stage.
      • Drug-resistant TB (DR-TB): Resistant to standard drugs due to incomplete or improper treatment.
    • Medicine Regimens:
      • Drug-sensitive TB: 6-month course- 2 months of HRZE (Isoniazid, Rifampicin, Pyrazinamide, Ethambutol) + 4 months of HR.
      • MDR-TB: Resistant to Isoniazid and Rifampicin; treated with 18–24-month regimen using Bedaquiline, Linezolid, Levofloxacin, Clofazimine, and Cycloserine.
      • Preventive Therapy: Isoniazid Preventive Therapy (IPT) for HIV-positive persons and close contacts of TB patients.

    Various Government Interventions for TB Prevention:

    • National TB Programme (NTP), 1962: India’s first structured TB-control effort; introduced BCG vaccination and district-level treatment services.
    • Revised National TB Control Programme (RNTCP), 1993: Adopted the DOTS strategy; achieved nationwide coverage by 2006, improving standardized treatment and cure rates.
    • Ni-kshay Portal, 2012: Launched as a national digital platform for TB case notification, tracking, and treatment monitoring across public and private sectors.
    • Ni-kshay Poshan Yojana, 2018: Introduced nutritional support of ₹500 per month to all notified TB patients through Direct Benefit Transfer (DBT).
    • National Strategic Plan for TB Elimination (2017–2025): Implemented in phased manner; structured around Detect, Treat, Prevent, Build, promoting CBNAAT/Truenat and decentralised care.
    • National TB Elimination Programme (NTEP), 2020: Renamed and upgraded from RNTCP; targets TB elimination by 2025 with universal free diagnostics, treatment, and surveillance.
    • Ni-kshay Sampark Helpline, 2023: Launched as a nationwide toll-free platform for patient counselling, treatment support, and follow-up.
    • Ni-kshay Mitra Initiative, 2022: Enabled individuals, NGOs, corporates to adopt TB patients for nutritional and diagnostic support under the Pradhan Mantri TB Mukt Bharat Abhiyan framework.
    • TB Mukt Bharat Abhiyan, 2024: Large-scale screening campaign covering 19 crore individuals; detected 24.5 lakh TB cases, including asymptomatic infections.
  • The Second Issue: On Surrogacy for a Second Child

    Introduction

    The Surrogacy (Regulation) Act, 2021 stipulates that an “intending couple” is eligible for surrogacy only if they do not have any surviving child, biological, adopted or via surrogacy, except where the child is physically or mentally challenged or has a life-threatening disorder.A petition has been filed before the Supreme Court by a couple facing secondary infertility who seek to use surrogacy to have a second child. Their argument: the law’s restriction interferes with the reproductive choices of citizens and treats primary and secondary infertility differently.

    What is the law’s objective and rationale

    1. Objective of the Act: The primary stated purpose is to prohibit commercial surrogacy, regulate fertility and surrogacy clinics, and protect surrogate mothers and children born through surrogacy.
    2. Eligibility restriction: Section 4(iii)(C)(II) mandates the ‘no surviving child’ condition for an intending couple.
    3. Rationale for restriction: The government’s position is that the use of another woman’s body for surrogacy demands strict regulation; therefore, limiting eligibility helps prevent exploitation and commercialization.
    4. Court’s interim view: The Supreme Court has indicated the restriction appears “reasonable” but is examining whether the ban on surrogacy for couples with a surviving child amounts to a violation of reproductive choice.

    How does the law differentiate primary and secondary infertility

    1. Secondary infertility defined: In this context, it refers to couples unable to conceive or carry a pregnancy to term despite having borne a child naturally earlier.
    2. Law’s silence on distinction: The Act does not expressly differentiate between primary and secondary infertility in defining “infertility” for eligibility. The petitioners argue the statute uses “infertility” generically and should be read to include secondary infertility.
    3. Effect of the distinction: As a result of the clause, a couple with one surviving (healthy) child is barred from surrogacy for a second child, even if they face medical infertility. The petition argues this amounts to unreasonable discrimination.

    Why is this matter significant now?

    1. Reproductive autonomy at stake: The case raises the question whether reproductive choice including whether and how many children to have falls under the fundamental right to privacy and reproductive autonomy (Article 21).
    2. Scale of the issue: Secondary infertility affects a substantial number of couples; the law’s bar effectively restricts access to surrogacy for many intending parents. The article emphasises that restricting access solely because a couple already has a child may not align with the law’s stated objective.
    3. Precedents of regulation being diluted: The Court recently relaxed age restrictions for couples who had frozen embryos prior to the law’s enactment, signalling willingness to interpret surrogacy law expansively.
    4. Contradiction with other family-related rights: There is no law in India capping the number of children a person may have naturally; yet, the surrogacy law imposes a “one-child existing” rule. This invites scrutiny of rational basis for differentiation.

    What are the potential implications of a broader interpretation”

    1. Facilitating access: A more expansive reading allowing surrogacy for intending parents would align the law with reproductive autonomy and reduce arbitrary differentiation.
    2. Safeguard against exploitation: The law can maintain its core safeguards against commercialisation and exploitation while enabling access for medically infertile couples seeking a second child.
    3. Policy coherence: It would harmonise the surrogacy statute’s eligibility norms with the lack of statutory restriction on the number of natural children and prevent unjust exclusion of couples.
    4. Legal precedent: A favourable interpretation could open up examination of other eligibility criteria under the Act (such as age or marital status) in light of constitutional rights.

    What are the counter-arguments and concerns?

    1. Risk of commercial surrogacy revival: Critics argue liberalising eligibility may inadvertently open doors to exploitation of surrogate mothers and a resurgence of commercial surrogacy in disguised form.
    2. Resource and monitoring constraints: Greater eligibility implies more oversight burden on regulatory infrastructure (ART clinics, surrogacy boards, monitoring of insurance/compensation).
    3. State interest in regulation: The restriction can be defended as within the State’s margin of appreciation to regulate surrogacy in public interest, preserving dignity of women and children.
    4. Potential slippery slope: Expanding eligibility might raise questions about single individuals, LGBTQ+ couples or live-in partners accessing surrogacy, aspects the law currently restricts.

    Conclusion

    The surrogacy debate in India reflects the evolving tension between state regulation and personal autonomy. While the law rightly seeks to prevent exploitation and commercialisation, it must not overlook the constitutional promise of reproductive freedom and equality. A more inclusive, rights-based interpretation, sensitive to medical realities like secondary infertility, would uphold both ethical safeguards and individual dignity, aligning the law with India’s vision of gender justice and compassionate governance.

    Value Addition: Surrogacy Law in India

    Legal Framework:

    Surrogacy (Regulation) Act, 2021

    • Objective: Regulate surrogacy procedures, prohibit commercial surrogacy, and ensure ethical practices in assisted reproduction.
    • Type allowed: Only altruistic surrogacy (no monetary compensation except medical expenses and insurance).
      • Assisted Reproductive Technology (Regulation) Act, 2021
    • Objective: Regulate ART clinics and banks; maintain records, screening, and ethical standards for gamete donation and IVF processes.
    • Together, these Acts create a twin legal framework governing all forms of medically assisted reproduction in India.

    Key Provisions of the Surrogacy (Regulation) Act, 2021

    1. Eligibility of intending couple:
      • Must be Indian citizens, legally married, and aged:
        • Husband: 26–55 years
        • Wife: 23–50 years
      • Must possess a certificate of infertility from a District Medical Board.
      • Must not have any surviving child (biological, adopted, or through surrogacy), except if the child is mentally/physically challenged or suffers a life-threatening disorder.
    2. Eligibility of surrogate mother:
      • Must be a married woman with a child of her own.
      • Age limit: 25–35 years.
      • Can act as a surrogate only once in her lifetime.
      • Must be a close relative of the intending couple.
      • Must obtain a certificate of medical and psychological fitness.
    3. National and State Surrogacy Boards: Oversee implementation, formulate policies, and ensure ethical compliance.
    4. Penal provisions:
      • Commercial surrogacy, sale/purchase of human embryos, and exploitation of surrogate mothers attract imprisonment up to 10 years and fine up to ₹10 lakh.

    Objectives and Rationale

    1. Prevent commercial exploitation: Protects poor women from being coerced into surrogacy for financial gain.
    2. Ensure child welfare: Guarantees the child’s legal status and parentage from birth.
    3. Promote ethical medical practices: Prevents unregulated fertility clinics and misuse of technology.
    4. Align with constitutional morality: Balances individual reproductive rights with social ethics and public health considerations.

    Judicial and Policy Developments

    1. SC observations (2023–2025):
      • Examining secondary infertility cases to test whether barring surrogacy for a second child violates reproductive autonomy under Article 21.
      • Previously allowed age relaxation for couples with frozen embryos prior to enactment of the Act.
    2. Delhi High Court (2023): Directed the government to reconsider rules preventing single women or widows from accessing surrogacy, citing discrimination concerns.
    3. Policy evolution: Shift from the 2015 ban on foreign commercial surrogacy to a 2021 framework permitting only altruistic domestic surrogacy.

    PYQ Relevance

    [UPSC 2023] Explain the constitutional perspectives of Gender Justice with the help of relevant constitutional provisions and case laws.

    Linkage: This question is key as it tests understanding of Articles 14, 15 and 21 on women’s equality and autonomy. This is central to debates like the Surrogacy Act 2021, which restricts reproductive choice and raises issues of bodily rights and gender justice.

  • [pib] Swasth Nari, Sashakt Parivar Abhiyaan (SNSPA)

    Why in the News?

    The Union Health Ministry has achieved three GUINNESS WORLD RECORDS titles under the “Swasth Nari, Sashakt Parivar Abhiyaan (SNSPA)”, highlighting India’s leadership in women’s health and preventive care.

    Guinness World Records Achieved

    • Most people registered on a health care platform in one month: 3.21 crore (3,21,49,711).
    • Most people signed up for breast cancer screening in one week: 9.94 lakh (9,94,349).
    • Most people signed up for vital signs screening online in one week (State level): 1.25 lakh (1,25,406).

    These records reflect unprecedented participation across India’s digital health platforms under the Ayushman Bharat initiative.

    About Swasth Nari, Sashakt Parivar Abhiyaan (SNSPA):

    • Objective: Strengthen women’s, children’s, and family health services, focusing on rural, tribal, and underserved regions.
    • Launch: Introduced on 17 September 2025 by the PM, jointly led by Ministry of Health and Family Welfare and the Ministry of Women and Child Development.
    • Scale: Over 10 lakh health camps at Ayushman Arogya Mandirs, Community Health Centres (CHCs), and District Hospitals.
    • Screenings: Anaemia, hypertension, diabetes, TB, breast and cervical cancers, sickle cell disease, reproductive health conditions.
    • Services offered: Maternal, child, adolescent health including antenatal care, immunisation, nutrition counselling, menstrual hygiene, mental health, lifestyle awareness.
    • Digital Monitoring: SASHAKT portal ensures real-time data tracking and transparency.
    • Jan Bhagidaari: Collaboration with private hospitals, SHGs, Anganwadis, Panchayati Raj institutions, volunteers.
    • Tribal Focus: Specialised medical services and tailored counselling for remote and tribal areas.

    What is Rashtriya Poshan Maah?

    • Overview: Part of POSHAN Abhiyaan (National Nutrition Mission); celebrated annually since 2018.
    • 2025 Edition: 8th Poshan Maah, aligned with SNSPA for synergised impact.
    • Aim: Mobilise communities to improve nutrition of children, pregnant women, lactating mothers, and adolescent girls.
    • Activities: Poshan Panchayats, health and nutrition camps, recipe demos, rallies, school-Anganwadi outreach, Jan Andolan approach.
    • Focus Areas (2025):
      • Anaemia Mukt Bharat and micronutrient awareness.
      • Complementary feeding practices for infants and toddlers.
      • Poshan-Vatika (nutri-gardens) for food security.
      • Promotion of traditional and regional diets for sustainable nutrition.
    [UPSC 2024] With reference to the ‘Pradhan Mantri Surakshit Matritva Abhiyan’, consider the following statements:

    1. This scheme guarantees a minimum package of antenatal care services to women in their second and third trimesters of pregnancy and six months post-delivery health care service in any government health facility.

    2. Under this scheme, private sector health care providers of certain specialities can volunteer to provide services at nearby government health facilities.

    Which of the statements given above is/are correct?

    Options: (a) 1 only (b) 2 only* (c) Both 1 and 2 (d) Neither 1 nor 2


  • [25th October 2025] The Hindu Op-ed: Respect the health rights of India’s children

    PYQ Relevance

    [UPSC 2020] In order to enhance the prospects of social development, sound and adequate health care policies are needed particularly in the fields of geriatric and maternal health care. Discuss.

    Linkage: Just as maternal and geriatric health require targeted policies, this article highlights the urgent need for child specific pharmaceutical regulation, reinforcing that inclusive social development demands age-segmented health care frameworks addressing the unique vulnerabilities of each group.

    Mentor’s Comment

    The tragic deaths of 25 children in Madhya Pradesh due to contaminated cough syrup have reignited a critical debate on India’s regulatory failure in child health and pharmaceutical safety. The incident exposes deep gaps in monitoring, quality control, and the larger question of how India safeguards its youngest citizens’ right to health. For UPSC aspirants, this issue links to public health governance (GS-2), ethical administration (GS-4), and inclusive growth (GS-3), all central to understanding India’s social contract with its people.

    Why in the News?

    Twenty five children lost their lives after consuming contaminated cough syrup, a tragedy that shocked the nation. The pediatrician involved reportedly received a ₹2.54 lakh commission for prescribing the syrup, raising questions about medical ethics, accountability, and the systemic failure of regulation. This is not an isolated case, since 2022, contaminated syrups from India have caused deaths in Gambia, Uzbekistan, Indonesia, and Cameroon, denting India’s image as the “pharmacy of the Global South.” The issue marks a repeated failure of quality control and enforcement, despite India having one of the largest pharmaceutical industries in the world.

    Where the Focus Needs to Be

    1. Regulatory framework: The emphasis must shift from blame to building robust regulatory architecture for the distribution of pediatric medicines.
    2. Child health protection: India must uphold its constitutional commitment under Article 39(f), ensuring children’s right to health and development.
    3. Legal ecosystem: Existing laws, such as the Pre-Conception and Pre-Natal Diagnostic Techniques Act and National Policy for Children 2013, must evolve to cover medicine safety for children.

    How Inadequate Oversight Endangers Children

    1. Weak pharmacovigilance: Insufficient clinical data and lack of dedicated pediatric testing result in drugs for adults being extrapolated for children.
    2. Dosage disparity: Absence of age-specific dosage guidelines often leads to overmedication and severe side effects.
    3. Special needs ignored: Pediatric pharmacology demands unique formulations, but most drugs are designed with adults as the reference.
    4. Ethical breach: The commission based medical practice further erodes trust, especially when children’s lives are at stake.

    What the Global Framework Teaches India

    1. Regulatory precedents: The European Union’s Paediatric Use Marketing Authorisation and the U.S. Best Pharmaceuticals for Children Act (BPCA) mandate pediatric testing for all drugs.
    2. Holistic approach: These frameworks ensure drug safety through clinical data collection, financial incentives for manufacturers, and legal enforcement.
    3. Indian gap: India lacks such comprehensive laws; existing rules focus only on general health safety, not pediatric-specific provisions.

    Why Pediatric Medicines Need Special Policy Attention

    1. Essential medicine concept: The WHO defines essential medicines as those meeting priority health needs. Pediatric formulations should be an integral part of this.
    2. Affordability: Without public support, many families cannot afford safe alternatives, forcing them to buy untested drugs.
    3. Domestic R&D: India’s dependency on adult-tested formulations highlights the absence of child focused pharmaceutical innovation.
    4. Education and regulation: Pharmacists and caregivers need training to ensure proper dosage and drug choice.

    How India Can Reform Pediatric Drug Policy

    1. Zero tolerance on contamination: Strong penalties and criminal accountability for substandard and spurious drugs.
    2. Independent regulator: A separate Pediatric Drug Safety Division within CDSCO (Central Drugs Standard Control Organisation).
    3. Integrated surveillance: Real time data monitoring for adverse pediatric drug reactions through digital reporting.
    4. International benchmarking: Alignment of India’s pediatric drug policy with WHO and OECD standards.
    5. Public awareness: Dissemination of safety information to parents, caregivers, and schools.

    Need for India Data

    1. Evidence based policy: India must base its pediatric drug policy on domestic child health data rather than extrapolations from adult studies or foreign datasets.
    2. Malnutrition link: Toxicity of contaminated syrups is worsened by underlying malnutrition, emphasizing a multi sectoral child health approach.

    Conclusion

    India’s children represent 39% of its population, yet policy neglect leaves them vulnerable to unsafe drugs and unethical practices. The current crisis is not just about regulatory lapses but about violating the fundamental right to health and life under Article 21. India must institutionalize a child-specific pharmaceutical policy, backed by strict monitoring, ethical medical practices, and international standard oversight. Ensuring safe, affordable, and regulated pediatric medicines is not merely a policy choice, it is a moral obligation and constitutional duty.

  • PM Schools for Rising India (PM SHRI) Scheme

    Why in the News?

    The Kerala government has formally signed the PM Schools for Rising India (PM-SHRI) agreement with the Union Ministry of Education, seeking approximately ₹1,446 crore to modernize government schools across the State.

    About the PM-SHRI Scheme:

    • Objective: To upgrade and modernize government schools as model institutions of quality education aligned with New Education Policy, 2020.
    • Purpose: Promote inclusive, equitable, and holistic education, integrating digital tools, environmental awareness, and vocational learning.
    • Overview: Launched in 2022 by the Ministry of Education as a Centrally Sponsored Scheme.
    • Scale & Duration: Targets 14,500 schools across India from 2022–23 to 2026–27, after which states will maintain benchmarks independently.
    • Funding Pattern: 60:40 (Centre: States/UTs with legislature), 90:10 (North-Eastern & Himalayan States), and 100% Central assistance (UTs without legislature).

    Key Features of PM-SHRI Schools:

    • Holistic Learning: Focus on creativity, collaboration, communication, and critical thinking beyond rote academics.
    • Pedagogical Shift: Promotes experiential, inquiry-driven, and multilingual education with art and technology integration.
    • Infrastructure Upgradation: Includes Smart Classrooms, Integrated Science & Computer Labs, Vocational/Skill Labs, Atal Tinkering Labs, and Digital Libraries.
    • Green Practices: Encourages solar power use, waste recycling, rainwater harvesting, and organic gardening to create sustainable campuses.
    • Assessment Reform: Moves from memorization to competency-based evaluation, measuring conceptual understanding and application.
    • Innovation Focus: Acts as incubators of educational innovation, influencing reforms across India’s public school system.

    Selection and Monitoring Mechanism:

    • Three-Stage Process:
      • Stage 1MoU signed by States/UTs committing to NEP-aligned reforms.
      • Stage 2 – Identification of eligible schools using UDISE+ data.
      • Stage 3Challenge Mode competition reviewed by an Expert Committee headed by the Education Secretary.
    • Monitoring System: Implemented via School Quality Assessment Framework (SQAF) evaluating academic, infrastructural, and administrative standards.
    • Accountability: Continuous digital evaluation, reporting, and performance tracking ensure transparency and sustained improvement.
    [UPSC 2017] What is the purpose of Vidyanjali Yojana?

    1. To enable the famous foreign campuses in India.

    2. To increase the quality of education provided in government schools by taking help from the private sector and the community.

    3. To encourage voluntary monetary contributions from private individuals and organizations so as to improve the infrastructure facilities for primary and secondary schools.

    Select the correct answer using the code given below:

    Options: (a) 2 only *  (b) 3 only (c) 1 and 2 only (d) 2 and 3 only


  • [10th October 2025] The Hindu Op-ed: India’s mental health crisis, the cries and scars

    PYQ Relevance:

    [UPSC 2023] Explain why suicide among young women is increasing in Indian Society.

    Linkage: Mental distress is deeply intertwined with societal issues like increasing suicide rates among young women, poverty, marginalization, and the impact of modernization and urbanization.

    Introduction:

    The National Crime Records Bureau’s Accidental Deaths and Suicides in India (ADSI) 2023 report recorded 1,71,418 suicides, a marginal 0.3% rise from 2022. While the suicide rate per lakh population declined slightly, absolute numbers remain high, underscoring a deep social, economic, and psychological crisis.

    National Data and Trends as per ADSI, 2023:

    1. Demographics: Men constituted 72.8% of suicides in 2023.
    2. Leading Causes: Family problems: 31.9%; Illness: 19%; Substance abuse: 7%; Relationship and marriage-related issues: around 10% combined.
    3. Regional Variation: The Andaman and Nicobar Islands, Sikkim, and Kerala had the highest suicide rates, while Maharashtra, Tamil Nadu, Madhya Pradesh, Karnataka, and West Bengal together accounted for over 40% of all cases.
    4. Urban vs Rural: Cities reported consistently higher suicide rates than rural areas, reflecting the psychological stress of urbanisation and competition.

    Farmer Suicides and Rural Distress:

    1. Farmer deaths: 10,786 suicides (6.3% of total) in 2023, concentrated mainly in Maharashtra and Karnataka.
    2. Long-term pattern: Over 1,00,000 farmers have taken their lives since 2014. Between 1995 and 2015, nearly 2,96,000 deaths were linked to debt, market volatility, and institutional neglect.
    3. Underlying causes: Debt, crop failure, inadequate price support, and the absence of reliable social safety nets.
    4. Invisible victims: Homemakers and caregivers, particularly women, face rising rates of depression and domestic stress but remain underrepresented in official data.

    Student Suicides in India:

    • Rising Trend: Students account for 6–8.1% of all suicides (NCRB data). In 2023, there were 13,892 student suicides, a 65% rise over the decade, outpacing the national average increase.
    • Major Causes: Academic pressure, parental expectations, toxic competition, and poor mental health infrastructure are leading contributors.
    • Psychological Impact: Surveys show high levels of anxiety, depression, and distress, with notable gender disparities in emotional well-being.

    Magnitude of Mental Illness in India:

    1. Estimated burden: Nearly 230 million Indians live with mental disorders ranging from depression and anxiety to bipolar disorder and substance use.
    2. Treatment gap: 70–92% of individuals with severe illness receive no formal care.
    3. Lifetime prevalence: 10.6%, according to national health data.
    4. Global comparison: WHO estimates India’s suicide rate at 16.3 per 1,00,000, significantly higher than the global average.

    Value Addition:

    India’s Mental Health Governance and Legal Framework:

    • Mental Healthcare Act, 2017:
      1. Guarantees the right to affordable, quality mental health care.
      2. Decriminalises suicide and mandates insurance coverage for psychiatric illnesses.
      3. Upholds patient dignity and autonomy under Article 21 of the Constitution.
    • Judicial reinforcement: In Sukdeb Saha vs State of Andhra Pradesh (2025), the Supreme Court reaffirmed mental health as a fundamental right, compelling state accountability.
    • District Mental Health Programme (DMHP): Covers 767 districts, expanding access to outpatient services, suicide prevention, and counselling.
    • Tele MANAS Helpline: A 24×7 service offering over 20 lakh tele-counselling sessions, particularly beneficial in underserved regions.

    Supreme Court Intervention:  Sukdeb Saha vs. State of Andhra Pradesh (2025):

    • Overview: The Supreme Court invoked Articles 32 and 141 to issue 15 binding “Saha Guidelines” addressing student suicides and mental health governance in educational institutions.
    • Key Judgment: It upheld mental health as an integral component of the right to life.
    • Key Guidelines include:
      1. Policy Mandate: All institutions must adopt a mental health policy consistent with UMMEED, MANODARPAN, and the National Suicide Prevention Strategy.
      2. Counseling Requirement: Appointment of one certified mental health counselor in every institution with 100+ students.
      3. Academic Practices: Ban on batch segregation, public shaming, and unrealistic academic targets.
      4. Helpline Visibility: Mandatory display of Tele-MANAS and other helpline numbers in classrooms, hostels, and websites.
      5. Staff Training: Biannual mental health sensitization for teachers and administrators on crisis response.
      6. Inclusivity Measures: Institutions must ensure non-discriminatory support for SC/ST/OBC/EWS, LGBTQ+, and disabled students.
      7. Crisis Management: Establish confidential reporting systems for ragging, discrimination, and assault, with immediate counseling access.
      8. Preventive Steps: Control access to common means of suicide (e.g., rooftops, ceiling fans) and promote interest-based career counseling.

    Systemic Gaps and Institutional Failures:

    1. Workforce shortage: Only 0.75 psychiatrists and 0.12 psychologists per 1,00,000 population, below WHO’s minimum of 1.7 psychiatrists and far from the ideal of 3.
    2. Underfunding: Mental health receives only 1.05% of India’s health budget, compared to 8–10% in countries like Australia, Canada, and the UK.
    3. Policy–practice gap:
      • The Mental Healthcare Act (2017) decriminalised suicide and guaranteed the right to care.
      • The National Suicide Prevention Strategy (2022) targeted a 10% reduction in suicides.
      • However, implementation remains weak, and suicides continue to rise.
    4. Non-functional initiatives:
      • The Manodarpan school-based support scheme remains largely inactive.
      • ₹270 crore allocated for mental health is largely unspent.

    Persistent Challenges:

    1. Treatment Gaps: 70–92% of individuals with common disorders like depression and anxiety remain untreated.
    2. Infrastructure Deficits: Inadequate availability of psychotropic medicines and rehabilitation services, which meet less than 15% of actual demand.
    3. Stigma and Awareness: Over 50% of Indians still attribute mental illness to personal weakness or shame, limiting early intervention.
    4. Workforce Urban Bias: Mental health professionals remain concentrated in cities, leaving rural areas, where 70% of India’s population lives, largely unserved.

    Steps to Strengthen India’s Mental Health System: Way Forward

    1. Budget Expansion: Raise mental health allocation to at least 5% of total health spending, ensuring resources for workforce, infrastructure, and medicine.
    2. Workforce Development: Train and deploy mid-level mental health providers to fill rural gaps and meet WHO’s minimum density.
    3. Integration: Embed mental health into primary health care and universal insurance coverage.
    4. Monitoring: Create a cascade-based national monitoring system to track outcomes, ensure accountability, and guide funding.
    5. Anti-Stigma Campaigns: Institutionalise mental health education in schools and workplaces, aiming for 60% literacy coverage by 2027.
    6. Cross-Ministerial Coordination: Establish a unified framework linking health, education, social justice, and labour for cohesive policy execution.
  • [pib] PM-SETU Scheme

    Why in the News?

    PM has launched the Pradhan Mantri Skilling and Employability Transformation through Upgraded ITIs (PM-SETU) Scheme to modernize India’s Industrial Training Institutes (ITIs) into industry-aligned centers of excellence.

    About the PM-SETU Scheme:

    • Overview: Centrally Sponsored Scheme under the Ministry of Skill Development & Entrepreneurship (MSDE).
    • Objective: Upgrade 1,000 Government ITIs into modern, industry-linked institutions that address evolving global skill demands.
    • Financing: Supported by the World Bank and Asian Development Bank (ADB); co-funded by Centre, States, and Industry.
    • Implementation Model: Operates on a Hub-and-Spoke structure
      • 200 Hub ITIs act as Centres of Excellence.
      • 800 Spoke ITIs extend outreach and training access across districts.
    • Target: Skill 20 lakh youth over five years through new and revamped programs.

    Key Features:

    • Industry Partnership: Each cluster managed by a Special Purpose Vehicle (SPV) with an Anchor Industry Partner, ensuring outcome-based, employment-linked training.
    • Curriculum Reform: New demand-driven, industry-aligned courses and flexible pathways — diplomas, short-term modules, and executive programs.
    • Infrastructure Modernization:
      • Advanced machinery, incubation and innovation centres, and production units in hub ITIs.
      • Integration of placement services and trainer-training facilities.
    • Centres of Excellence (NCOEs): Upgradation of 5 National Skill Training Institutes (NSTIs) at Bhubaneswar, Chennai, Hyderabad, Kanpur, and Ludhiana into global-standard NCOEs with international collaboration.
    • Pilot Phase: Begins with Patna and Darbhanga ITIs (Bihar) as the first upgraded hubs.
    • Youth Empowerment Focus: Links skilling with innovation, startups, and MSMEs to create self-employment opportunities and strengthen India’s human-capital base.

    Also in News: National Scheme for ITI Upgradation & NCOEs

    • Cabinet-approved (May 2025) companion initiative with an outlay of ₹60,000 crore:
      • Central Share: ₹30,000 cr;  State: ₹20,000 cr;  Industry: ₹10,000 cr.
      • 50 % of the Central share co-financed by World Bank and ADB.
    • Purpose: Upgrade 1,000 ITIs and establish 5 NCOEs as Government-owned, Industry-managed skill institutions.
    • Features:
      • Need-based investment flexibility for each ITI.
      • Training-of-Trainers (ToT) infrastructure upgrade and training for 50,000 trainers.
      • Enhanced alignment of local workforce supply with MSME and industrial demand.
      • Introduction of an industry-led SPV model for better accountability and course relevance.


    [UPSC 2018] With reference to Pradhan Mantri Kaushal Vikas Yojana, consider the following statements:

    1. It is the flagship scheme of the Ministry of Labour and Employment.

    2. It, among other things, will also impart training in soft skills, entrepreneurship, financial and digital literacy.

    3. It aims to align the competencies of the unregulated workforce of the country to the National Skill Qualification Framework.

    Which of the statements given above is/are correct?

    Options: (a) 1 and 3 only (b) 2 only (c) 2 and 3 only* (d) 1, 2 and 3