💥Mains Ready By December. Smash Mains & Smash PYQ Admissions Open

Subject: Health

  • Mid day Meal Scheme

    A parliamentarian has recently asked the government to re-start the mid-day meals in reopening schools and to ensure that the meals provided are cooked and nutritious.

    What is the Mid-Day Meal Scheme?

    • The Midday Meal Scheme is a school meal program designed to better the nutritional standing of school-age children nationwide.
    • It was launched in the year 1995.
    • It supplies free lunches on working days for children in primary and upper primary classes in:
    1. Government, government aided, local body schools
    2. Education Guarantee Scheme, and alternate innovative education centres,
    3. Madarsa and Maqtabs supported under Sarva Shiksha Abhiyan, and
    4. National Child Labour Project schools run by the ministry of labour
    • The Scheme has a legal backing under the National Food Security Act, 2013.

    Objective: To enhance the enrolment, retention and attendance and simultaneously improve nutritional levels among school going children studying in Classes I to VIII

    History of the scheme

    • In 1925, a Mid Day Meal Programme was introduced for disadvantaged children in Madras Municipal Corporation.
    • By the mid-1980s three States viz. Gujarat, Kerala and Tamil Nadu and the UT of Pondicherry had universalized a same scheme with their own resources for children studying at the primary stage.
    • In 2001, the Supreme Court asked all state governments to begin this programme in their schools within 6 months.

    Features: Calorie approach

    • Primary (1-5) and upper primary (6-8) schoolchildren are currently entitled to 100 grams and 150 grams of food grains per working day each.
    • It also include adequate quantities of micronutrients like iron, folic acid, Vitamin-A, etc.
    • The calorific value of a mid-day meal at various stages has been fixed at a minimum:
    Calories Intake Primary Upper Primary
    Energy 450 calories 700 calories
    Protein 12 grams 20 grams


    Why in news?

    • The flagship report of The State of Food Security and Nutrition in the World 2020 estimated that as of April 2020 369 million children globally were losing out on school meals, a bulk of whom were in India.
    • As many as 116 million children — actually, 116 million hungry children — is the number of children impacted due to indefinite school closure during the pandemic.

    Why discuss it now?

    • The recent Global Hunger Index (GHI) report for 2020 ranks India at 94 out of 107 countries and in the category ‘serious’, behind our neighbours Pakistan, Bangladesh and Nepal.
    • The index is a combination of indicators of undernutrition in the population and wasting (low weight for height), stunting (low height for age), and mortality in children below five years of age.

    What measures were resorted to counter this?

    • In March and April 2020 the GoI had announced that the usual hot-cooked mid-day meal or an equivalent food security allowance/dry ration would be provided to all eligible school-going children even during vacation.
    • Nearly three months into this decision, States were still struggling to implement this.

    What lies ahead?

    • Across the country and the world, innovative learning methods are being adopted to ensure children’s education outcomes.
    • The GHI report calls for effective delivery of social protection programmes.
    • With continuing uncertainty regarding the reopening of schools, innovation is similarly required to ensure that not just food, but nutrition is delivered regularly to millions of children.
    • For many of them, that one hot-cooked meal was probably the best meal of the day.


    UPSC 2022 countdown has begun! Get your personal guidance plan now! (Click here)
  • 13% reduction in air pollution deaths due to UJJAWALA Scheme

    Greater penetration and usage of LPG as a cooking fuel is estimated to have prevented at least 1.5 lakh pollution-related premature deaths in the year 2019 alone, according to the first independent impact assessment of the government’s flagship Ujjwala program.

    About the PM Ujjwala Yojana

    • Pradhan Mantri Ujjwala Yojana (PMUY) was launched in 2016, with the aim to provide Liquefied petroleum gas (LPG) connections to five crore women members of below poverty line (BPL) households in the first phase.
    • he scheme was expanded in April 2018 to include women beneficiaries from seven more categories (SC/ST, PMAY, AAY, Most backward classes, tea garden, forest dwellers, Islands).
    • In the second phase the target was expanded to eight crore LPG connections.

    Why was this scheme launched?

    • Indoor air pollution is also responsible for a significant number of acute respiratory illnesses in young children.
    • Providing LPG connections to BPL households will ensure universal coverage of cooking gas in the country.
    • This measure has empowered women and protected their health. It reduced drudgery and the time spent on cooking.
    • It will also provide employment for rural youth in the supply chain of cooking gas.

    Ujjwala 2.0

    • Under Ujjwala 2.0 migrant workers would no longer have to struggle to get address proof documents to get the gas connections.
    • Now migrant workers would only be required to submit a self-declaration of their residential address to get the gas connection.
    • Along with a deposit-free LPG connection, Ujjwala 2.0 will provide the first refill and a hotplate free of cost to the beneficiaries.

    Significance of Ujjwala 2.0

    • LPG infrastructure has expanded manifold in the country due to the Ujjwala scheme.
    • In the last six years, more than 11,000 new LPG distribution centres have opened across the country.
    • The LPG coverage in India is now very close to becoming 100 per cent.


    UPSC 2022 countdown has begun! Get your personal guidance plan now! (Click here)

  • TB’s steep socio-economic cost to women

    Context

    As India steadily steers its way through the pandemic to safer shores, we must foreground a disease which has been impacting our country for years, and disproportionately affecting women –  tuberculosis.

    Toll of TB

    • In India, the TB case fatality ratio increased from 17 per cent in 2019 to 20 per cent in 2020.
    • According to a joint report (2010-13) of the Registrar General of India and the Centre for Global Health Research, TB was the fifth-leading cause of death among women in the country, accounting for nearly 5 per cent of fatalities in women aged 30–69.

    How TB affects women more than men

    • Much steeper socio-economic price: While both men and women suffer the consequences of this debilitating disease, women patients pay a much steeper socio-economic price.
    • Beyond clinical metrics: From social ostracisation and lack of family support to the negative impact on marital prospects, women absorb the repercussions of TB beyond the clinical metrics.
    • Stigma also acts as a strong deterrent when it comes to health-seeking behaviour.
    • Fewer women, therefore, get included in the available cascade of care for TB.

    Measures by government

    • In 2019, the Health Ministry-Central TB Division developed a national framework for a gender-responsive approach to TB in India.
    • The document takes cognisance of the challenges faced by women in accessing treatment and offers actionable solutions.
    • Gender-responsive policy interventions: In December 2021, a parliamentary conference on ‘Women Winning Against TB’ was organised by the Ministry of Women and Child Development where gender-responsive policy interventions were discussed.
    • The Vice-President of India urged states to take proactive steps such as ensuring nutritional support to women and children and the doorstep delivery of TB services, especially for women from socio-economically weaker backgrounds.

    Suggestions

    1] Highlight the issue at the relevant forum

    • One, as elected representatives, we need to come together more to highlight the issue at all relevant forums and spaces.
    • These meetings see increased participation of women leaders from all walks of life in the community going forward.

    2] Strengthen counselling network

    • We need to strengthen counselling networks for women patients and their families.
    • Irrespective of where the patient seeks care – public or private sector – build the capacity of healthcare workers to educate the patient’s family about the importance of providing her a supportive environment during the course of her treatment.

    3] Nutritional needs

    • We need to ensure that the nutritional needs of women are being met.
    • Undernutrition is a serious risk factor for TB and research indicates such risks are higher for women.
    • It is commendable that the government, through Nikshay Poshan Yojana, has effectively provided a monthly benefit of Rs 500 to enable a nutritious diet for TB patients in the last few years.
    • For the 2020 cohort, the total amount paid under NPY via DBT has been over  Rs 200 crore.
    • Additionally, we can look to further strengthen inter-departmental coordination, wherein the Public Distribution System can explore appropriate linkages with relevant departments of the MoHFW and even include a protein-rich diet for TB patients.

    4] Amplify accurate TB messaging

    • At a community level, we must amplify accurate TB messaging and showcase how gender plays a role in determining the course of action on the ground.

    Conclusion

    These are universal problems that must transcend gender binaries. Only when equitable solutions are offered to vulnerable sections of society will we be able to realise the dream of TB-Mukt Bharat.

    UPSC 2022 countdown has begun! Get your personal guidance plan now! (Click here)


  • Maternal Mortality in India

    Kerala has yet again emerged on top when it comes to maternal and child health, with the State recording the lowest Maternal Mortality Ratio (MMR) of 30 (per one lakh live births) in the country.

    What is Maternal Mortality?

    • Maternal mortality refers to deaths due to complications from pregnancy or childbirth.
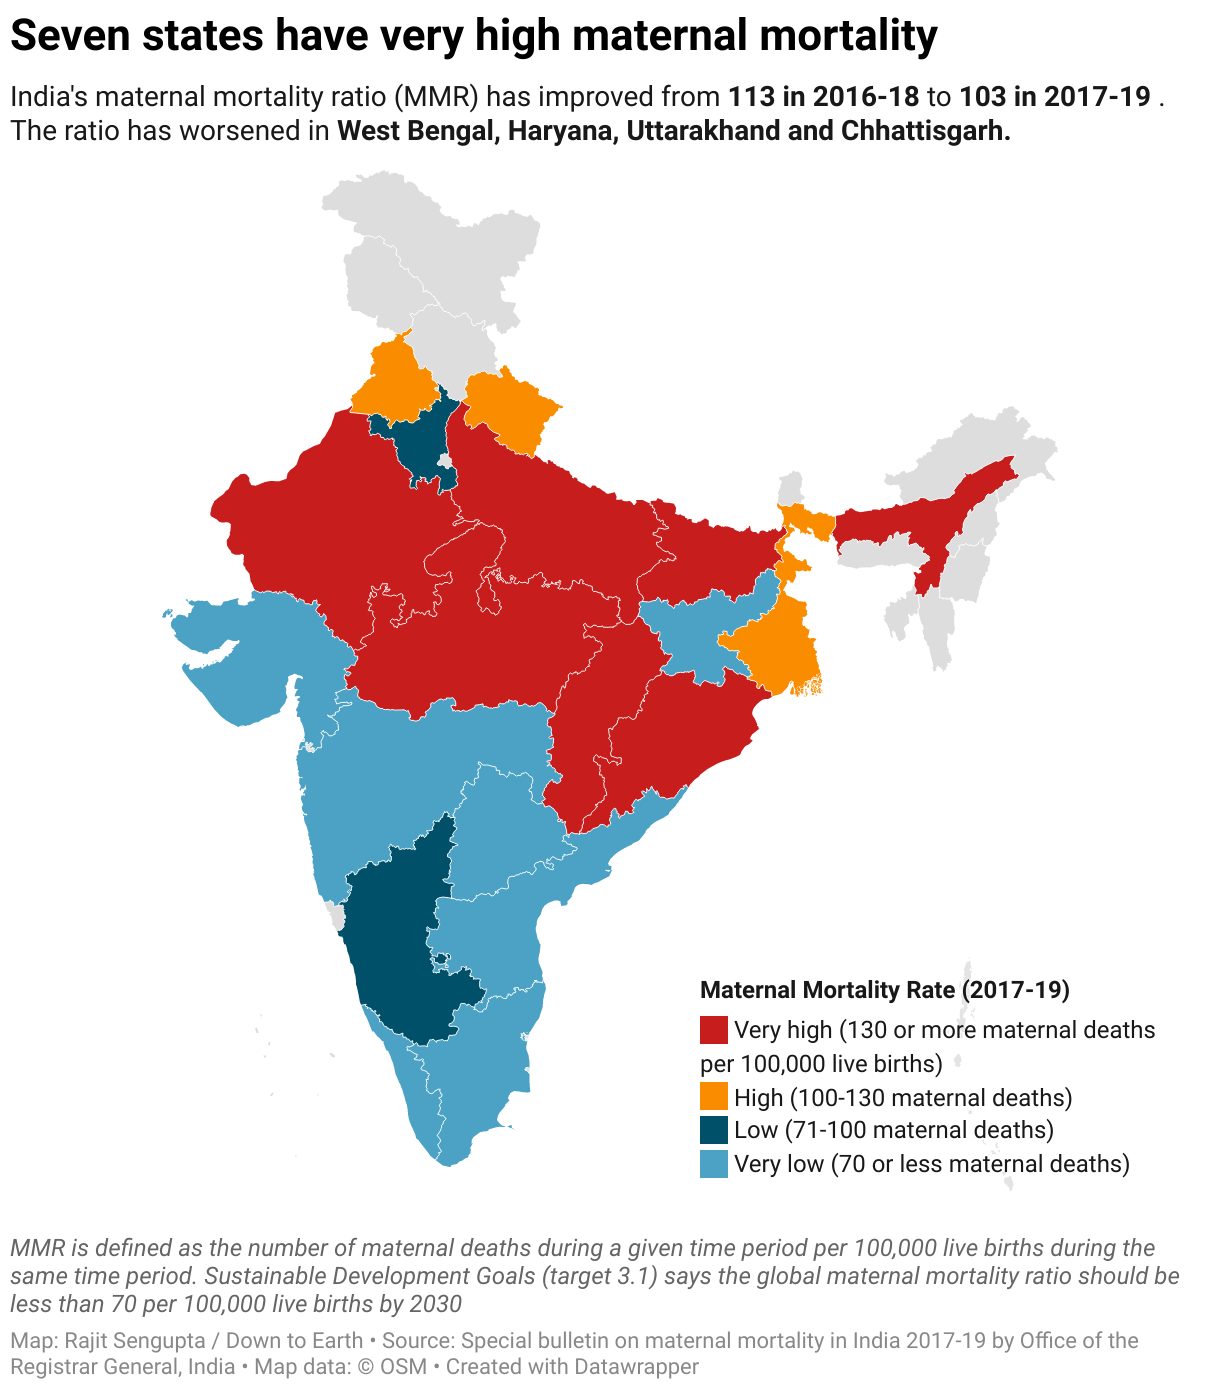
    • The maternal mortality ratio (MMR) is defined as the number of maternal deaths during a given time period per 100,000 live births during the same time period.
    • It depicts the risk of maternal death relative to the number of live births and essentially captures the risk of death in a single pregnancy or a single live birth.

    Trends in India

    • India’s maternal mortality ratio (MMR) has improved to 103 in 2017-19, from 113 in 2016-18.
    • Seven Indian states have very high maternal mortality. These are Rajasthan, Uttar Pradesh, Madhya Pradesh, Chhattisgarh, Bihar, Odisha and Assam.
    • The MMR is ‘high’ in Punjab, Uttarakhand and West Bengal. This means 100-130 maternal deaths per 100,000 live births.
    • It is ‘low’ in Haryana and Karnataka.
    • The states of Uttar Pradesh, Rajasthan and Bihar have seen the most drop in MMR.
    • West Bengal, Haryana, Uttarakhand and Chhattisgarh have recorded an increase in MMR over the last survey.

    Various determinants of maternal health in India

    UPSC 2022 countdown has begun! Get your personal guidance plan now! (Click here)

  • Tobacco and related issues in India

    Context

    Tobacco is a silent killer in our midst that kills an estimated 1.35 million Indians every year.

    The harm caused by tobacco

    • It is the use of tobacco as a result of which more than 3,500 Indians die every single day, as estimated by scientific studies.
    • It also comes at a heavy cost: an annual economic burden of ₹1,77,340 crore to the country or more than 1% of India’s Gross Domestic Product (GDP).

    How price and taxation of tobacco matters

    •  Research from many countries around the world including India shows that a price increase induces people to quit or reduce tobacco use as well as discourages non-users from getting into the habit of tobacco use.
    • There is overwhelming consensus within the research community that taxation is one of the most cost-effective measures to reduce demand for tobacco products.
    • There has been no significant tax increase on any tobacco product for four years in a row.
    • This is quite unlike the pre-GST years where the Union government and many State governments used to effect regular tax increases on tobacco products.
    • As peer-reviewed studies show, the lack of tax increase over these years has made all tobacco products increasingly more affordable.
    •  The absence of a tax increase on tobacco has the potential to reverse the reduction in tobacco use prevalence that India saw during the last decade and now push more people into harm’s way.
    •  It would also mean foregone tax revenues for the Government.

    Way forward

    • The Union Budget exercise is not the only opportunity to initiate a tax increase on tobacco products.
    • The Goods and Services Tax (GST) Council could well raise either the GST rate or the compensation cess levied on tobacco products especially when the Government is looking to rationalise GST rates and increase them for certain items.
    • For example, there is absolutely no public health rationale why a very harmful product such as the bidi does not have a cess levied on it under the GST while all other tobacco products attract a cess.
    • GST Council meetings must strive to keep public health ahead of the interests of the tobacco industry and significantly increase either the GST rates or the GST compensation cess rates applied on all tobacco products.

    Conclusion

    The aim should be to arrest the increasing affordability of tobacco products in India and also rationalise tobacco taxation under the GST.

    UPSC 2022 countdown has begun! Get your personal guidance plan now! (Click here)

  • What is ‘Front-of-Pack Labelling’ (FoPL)?

    The Food Safety and Standards Authority of India (FSSAI) will soon start labelling the front of packaged food products with Health Star Rating (HSR).

    What is FoPL?

    • In India, packaged food has had back-of-package (BOP) nutrient information in detail but no FoPL.
    • Counter to this, FoPL can nudge people towards healthy consumption of packaged food.
    • It can also influence purchasing habits.
    • The study endorsed the HSR format, which speaks about the proportions of salt, sugar, and fat in food that is most suited for consumers.
    • Countries such as the UK, Mexico, Chile, Peru, Hungary, and Australia have implemented FoPL systems.

    What warranted such rating in India?

    • Visual bluff: A lot of Indian consumers do not read the information available at the back of the packaged food item.
    • Burden of NCDs: Also, India has a huge burden of non-communicable diseases that contributes to around 5.87 million (60%) of all deaths in a year.
    • Healthy dietary choices: HSR will encourage people to make healthy choices and could bring a transformational change in the society.
    • Supreme court order: A PIL seeking direction to the government to frame guidelines on HSR and impact assessment for food items and beverages was filed in the Supreme Court in June 2021.

    Which category of food item will have HSR?

    • All packaged food items or processed food will have the HSR label.
    • These will include chips, biscuits, namkeen, sweets and chocolates, meat nuggets, and cookies.
    • However, milk and its products such as chenna and ghee are EXEMPTED as per the FSSAI draft notified in 2019.

    Will there be pushback from food industry?

    • Negative warning: Some experts opposed the use of the HSR model in India, suggesting that consumers might tend to take this as an affirmation of the health benefits rather than as a negative warning of ill effects.
    • Lack of awareness: This is significant because there is lack of awareness on star ratings related to consumer products in India.
    • Impact on Sale: Certain organisations fear it might affect the sale of certain food products.

    When will the rating come into force?

    • FSSAI’s scientific panel recommends voluntary implementation of HSR format from 2023 and a transition period of four years for making it mandatory.
    • FSSAI noted that the proposed thresholds are in alignment with the models implemented in other countries and ‘WHO population nutrient intake goals recommendations’.
    • FSSAI will analyse the nutritional information in 100 mg of packaged food.
    • The food safety compliance system licensing application portal will have a module for generating certificates wherein a licensee can enter details of a product.


    UPSC 2022 countdown has begun! Get your personal guidance plan now! (Click here)


    Back2Basics: Food Safety and Standards Authority of India (FSSAI)

    • The FSSAI is an autonomous body established under the Ministry of Health & Family Welfare, Government of India.
    • It has been established under the Food Safety and Standards Act, 2006 which is a consolidating statute related to food safety and regulation in India.
    • It is responsible for protecting and promoting public health through the regulation and supervision of food safety.
    • It is headed by a non-executive Chairperson, appointed by the Central Government, either holding or has held the position of not below the rank of Secretary to the Government of India.
  • Anti-microbial resistance needs urgent attention

    Context

    Ever since the pandemic struck, concerns have been raised about the improper use of antimicrobials amongst Covid-19 patients.

    Concern over anti-microbial resistance

    • The “Global burden of bacterial antimicrobial resistance in 204 countries and territories in 2019 (GRAM)” report, released last month, 4.95 million people died from drug-resistant bacterial infections in 2019, with 3,89,000 deaths in South Asia alone.
    • AMR directly caused at least 1.27 million of those deaths.
    • Lower respiratory infections accounted for more than 1.5 million deaths associated with resistance in 2019, making it the most burdensome infectious syndrome.
    • Amongst pathogens, E coli was responsible for the most deaths in 2019, followed by K pneumoniae, S aureus, A baumannii, S pneumoniae, and M tuberculosis.

    Concern for India

    • As per the yearly trends reported by the Indian Council of Medical Research since 2015, India reports a high level of resistance in all these pathogens, especially E coli and K pneumoniae.
    • Only a fraction of the Indian data, available through the WHO-GLASS portal, has been included in the GRAM report.
    • India has been reporting high levels of resistance to fluoroquinolones, cephalosporins and carbapenems across the Gram-negative pathogens that cause almost 70 per cent of infections in communities and hospitals.
    • Therefore, the Indian data on the AMR burden may not look very different from the estimates published in the report.
    • Now that we know that AMR’s burden surpasses that of TB and HIV, a sense of urgency in containing such resistance is called for.
    • With no new drugs in the pipeline for drug-resistant infections, time is running out for patients.

    Addressing AMR through a multipronged and multisectoral approach

    • Use existing antimicrobials judiciously: The urgency to develop new drugs should not discourage us from instituting measures to use the existing antimicrobials judiciously.
    • Improved infection control in communities and hospitals, availability and utilisation of quality diagnostics and laboratories and educating people about antimicrobials have proved effective in reducing antimicrobial pressure — a precursor to resistance.
    • The National Action Plan for AMR, approved in 2017, completes its official duration this year. The progress under the plan has been far from satisfactory.
    • There is enough evidence that interventions like infection control, improved diagnosis and antimicrobial stewardship are effective in the containment of AMR.

    Conclusion

    The GRAM report has underlined that postponing action could prove costly.

    UPSC 2022 countdown has begun! Get your personal guidance plan now! (Click here)

  • Need for integrated approach to power sector

    Context

    Electricity and development sectors need a more integrated approach to achieve the vision set forth in instruments such as the Union Budget that guide policy implementation at other administrative levels.

    Reduction in allocation

    • While the health sector witnessed a 16% increase in estimated Budget allocations from last year, medical and public health spending was reduced by 45% for 2022-23.
    • Budget estimates demonstrate intent, but the proof of the pudding lies in the actual expenditure which reiterates the need for greater attention to be paid to our health and education sectors.
    •  While the health sector was allocated ₹74,602 crore in 2021-22, the Government exceeded its spending by over ₹5,000 crore more (₹80,026 crore) on health, signalling a spike in demand, likely propelled by the ongoing COVID-19 pandemic.
    • Given this scenario, a less than ₹1,000 crore increase in the Budget Estimate (₹86,606 crore) in 2022-23 when compared with last year’s Revised Estimates (₹85,915 crore) appears incongruent with the Government’s aim of providing quality public health care at scale.

    Role of reliable energy

    • It is widely recognised that the availability of reliable electricity supply can improve the delivery of health and education services.
    •  74% of the targets of the Sustainable Development Goals are interlinked with universal access to reliable energy.
    •  Its reliability in terms of the number of hours that electricity is available steadily without any voltage fluctuations also plays a significant role in delivering services.
    •  Sometimes, multiple policies can complement each other to achieve the larger sectoral objectives.
    • For example, in Assam, the Energy Vision document that lays out the electricity and development outcomes is to be applied in tandem with the Solar Energy Policy 2017 that operationalises this vision via an action plan.

    Reasons for lack of integration of electrification in the development sector

    • The lack of integration of electrification requirements in development sector policy documents may be partly due to lack of information about electricity and development linkages, poor coordination mechanisms between the sectors and departments, and poor access to appropriate finance.
    • Even while electricity is considered, it is to the limited extent of being a one-time civil infrastructure activity rather than a continuous feature necessary for the day-to-day operations of these services.

    Way forward

    •  To successfully integrate electricity provisioning and maintenance, policy frameworks should include innovative coordination and financing mechanisms.
    • These mechanisms, while developing clear compliance mandates, must also allow sufficient room for flexibility to respond to local contexts.
    • Providing reliable electricity for health centres and schools should be the responsibility of centralised decision-making entities at the State or national level.
    • As India has witnessed with other cross-sectoral and centralised statistical, planning, and implementation data governance, diverse contexts must support oversight mechanisms that ensure data credibility.
    • Finance is largely unavailable to ensure reliable electricity supply to schools and health facilities.
    • Some directives, such as those governing the use of untied funds, need to be more flexible in allowing these facilities to prioritise providing reliable and sustainable electricity.

    Conclusion

    A successful policy outcome might be dependent on several invisible aspects that do not get the attention and funding necessary to aid in successful policy delivery. Electricity is one of them.

    UPSC 2022 countdown has begun! Get your personal guidance plan now! (Click here)

  • What are Eat Right Campuses?

    Four police stations of New Delhi district have been certified as ‘Eat Right Campus’ by the Food Safety and Standards Authority of India (FSSAI).

    Eat Right Campus

    • Eat Right India is a flagship mission of FSSAI, which aims at ensuring that the citizens of the country get safe and nutritious food.
    • The ‘Eat Right Campus’ initiative led by FSSAI aims to promote safe, healthy and sustainable food in campuses such as schools, universities, colleges, workplaces, hospitals, tea estates etc. across the country.
    • The objective is to improve the health of people and the planet and promote social and economic development of the nation.
    • The initiative is not mandatory to adopt.

    Evaluation Criteria

    • Benchmarks have been created on four different parameters based on which campuses are evaluated and certified as ‘Eat Right Campus’.
    • These parameters include
    1. Food safety measures, steps to ensure the provision of healthy, Environmentally sustainable food, and Building awareness to make the right food choices.
    2. These practices include mandatory steps such as licensing and registration of food service providers in the campus and compliance to food safety and hygiene standards as per Schedule 4 of the Food Safety and Standards (FSS) Act, 2006.

    Benefits of Eat Right Campus

    • It can provide immense benefits to the campus and the individuals on the campus not only in terms of health but also economics.
    • Safe, healthy, and sustainable food on the campus would reduce the incidence of food-borne illnesses, deficiency diseases, and non-communicable diseases among the people on the campus.
    • This means less absenteeism and loss of working hours and greater wellbeing, motivation, and productivity of people.
    • This would also reduce the burden of healthcare costs for the workplace, institution, hospital, jail, or tea estate.

    Back2Basics: Food Safety and Standards Authority of India (FSSAI)

    • The FSSAI is an autonomous body established under the Ministry of Health & Family Welfare, Government of India.
    • It has been established under the Food Safety and Standards Act, 2006 which is a consolidating statute related to food safety and regulation in India.
    • It is responsible for protecting and promoting public health through the regulation and supervision of food safety.
    • It is headed by a non-executive Chairperson, appointed by the Central Government, either holding or has held the position of not below the rank of Secretary to the Government of India.


    UPSC 2022 countdown has begun! Get your personal guidance plan now! (Click here)

  • Intensified Mission Indradhanush (IMI) 4.0 launched

    The Union Health Minister has launched the Intensified Mission Indradhanush (IMI) 4.0.

    About IMI 4.0

    • The IMI 4.0 will have three rounds and will be conducted in 416 districts (including 75 districts identified for Azadi ka Amrit Mahotsav) across 33 States and UTs, a Health Ministry statement said.
    • It will immensely contribute in filling the gaps and make lasting gains towards universal immunisation.
    • It will ensure that Routine Immunisation (RI) services reach the unvaccinated and partially vaccinated children and pregnant women” he said.

    What is Mission Indradhanush ?

    • With the aim to increase the full immunisation coverage, the PM launched Mission Indradhanush in December 2014.
    • It aimed to cover the partially and unvaccinated pregnant women and children in pockets of low immunisation coverage, high-risk and hard-to-reach areas and protect them from vaccine preventable diseases.
    • The first two phases of the Mission resulted in 6.7% increase in full immunisation coverage in a year.

    Aims and objectives

    • It aims to immunize all children under the age of 2 years, as well as all pregnant women, against eight vaccine-preventable diseases.
    • The diseases being targeted are diphtheria, whooping cough, tetanus, poliomyelitis, tuberculosis, measles, meningitis and Hepatitis B.
    • In 2016, four new additions have been made namely Rubella, Japanese Encephalitis, Injectable Polio Vaccine Bivalent and Rotavirus.
    • In 2017, Pneumonia was added to the Mission by incorporating the Pneumococcal conjugate vaccine under Universal Immunisation Programme


    UPSC 2022 countdown has begun! Get your personal guidance plan now! (Click here)